








Condition guide
Eversion Ankle Sprain
Injury or dysfunction involving ankle structures.

Eversion Ankle Sprain: Rehabilitating a Medial Ligament Injury
What Is an Eversion Ankle Sprain?
An eversion ankle sprain occurs when the foot rolls outward, overstretching or tearing the ligaments on the inner side of the ankle (primarily the deltoid ligament). This is different than in inversion ankle sprain, where the ankle rolls inward. Eversions sprains are less common and more severe than inversion sprains, as they often involve higher-force trauma.
Anatomy of the Deltoid Ligament Complex
Function
The deltoid ligament has a crucial role in ankle stabilization. The deltoid ligament is a primary stabilizer against eversion (outward rolling) and external rotation of the ankle. This ligament works with the bony architecture, such as the medial malleolus to prevent overstretching. The lateral malleolus also plays a crucial role in lateral ankle stability. Since the lateral malleolus drops lower than the medial malleolus, it works with the deltoid ligament to prevent eversion. The increase in lateral ankle stability makes eversion ankle sprains more rare, but more serious.
Deltoid Ligament Components
1. Superficial Deltoid Layer
- Function: resisting eversion
- Components:
- Tibiospring ligament
- Tibiocalcaneal ligament
- Posterior superficial tibiotalar ligament
- Tibionavicular ligament
- Vascularity: Moderate blood flow (from posterior tibial artery branches).
- Healing Implications:
- Better healing potential than deep layer due to richer vascular network.
- Grade I-II sprains often heal well with conservative care (bracing, PT).
2. Deep Deltoid Layer
- Function: resist rotational forces
- Components:
- Anterior tibiotalar ligament
- Posterior deep tibiotalar ligament
- Vascularity: Poor blood supply (relies on diffusion from synovial fluid).
- Healing Implications:
- Slower healing; prone to chronic instability if torn.
- Complete tears (Grade III) may require surgery if causing persistent instability.
Why Is This Important?
- Superficial tears: Typically heal in 4 to 6 weeks with protection.
- Deep tears: May take 8 to 12+ weeks and need prolonged rehab or surgical fixation.
Causes and Risk Factors
Eversion ankle sprains are often caused by:
- Awkward landings (e.g., jumping onto uneven surfaces).
- Sports collisions or tackles that push the foot laterally.
- For example, getting slide tackled in soccer.
- Overpronation (flat feet) during running/cutting.
- High-impact trauma, such as falls.
- Sudden twists
- Underlying ankle instability
Physiotherapy for Eversion Sprain Recovery
Deltoid ligament injuries in the ankle, though less common than lateral sprains, can lead to chronic instability if not properly managed. These injuries often occur in conjunction with ankle fractures or multi-ligament injuries. Managing the injury with physiotherapy early on is crucial for a smooth rehabilitation process and return to sport and daily activities.
Phase 1: Protection & Mobility (Weeks 0 to 2)
Goals:
- Reduce pain/swelling.
- Protect ligament healing.
- Prevent stiffness without stressing injured tissues.
1. Acute Management (First 72 Hours)
- RICE Protocol:
- Rest: Avoid weight-bearing (use crutches if painful to walk).
- Ice: 15 to 20 mins every 2 to 3 hours to reduce swelling.
- Compression: Elastic bandage or ankle brace (e.g., lace-up or rigid stirrup).
- Elevation: Keep ankle above heart level to minimize edema.
2. Early Mobility (Day 4 to 14)
- Ankle Pumps:
- Sit with leg extended; slowly pump ankle up/down 10 to 15 reps every 2 hours. Promotes circulation without strain.
- Toe Circles/Tracing Alphabet:
- Gentle clockwise/counterclockwise circles or "write" letters with toes. Maintains joint mobility.
- Non-Weight-Bearing (NWB) Stretches:
- Towel Stretch: Loop towel around foot; gently pull toes toward you (hold 15 to 30 sec). Stretches Achilles/calf safely.
3. Protection Strategies
- Bracing: Wear a walking boot or rigid brace if moderate/severe injury.
- Weight-Bearing: Progress from NWB → partial weight-bearing (PWB) only if pain-free.
Things to Avoid in Phase 1:
- Eversion motions (outward rolling).
- Stretching the inner ankle aggressively.
- Walking without support if painful.
Progression Criteria to Phase 2:
Minimal swelling/pain at rest.
Tolerates PWB in brace.
Restored 50% passive dorsiflexion/plantarflexion.
Phase 2: Strengthening & Stability (Weeks 2 to 6)
Goals:
- Restore strength in deltoid ligament and dynamic stabilizers.
- Improve balance/proprioception.
- Prepare for functional movements.
1. Strengthening Exercises
A. Resisted Ankle Motions (Band/Cable)
- Inversion (3x15 reps): Anchor band to a fixed object; pull foot inward against resistance.
- Targets tibialis posterior (key stabilizer for medial arch).
- Eversion (3x15 reps): Band around forefoot; push outward (controlled).
- Strengthens peroneals to balance forces on deltoid ligament.
B. Calf Raises (2x10 to 15 reps)
- Double-leg → single-leg progression (on flat ground → step).
- Restores gastrocnemius/soleus strength for push-off stability.
C. Hip/Core Stability
- Clamshells (3x15 reps): Side-lying, resist band at knees to strengthen gluteus medius.
- Dead Bugs (3x10 reps/side): Core activation with controlled limb movements.
2. Balance & Proprioception
- Single-Leg Stance (30 sec → 1 min): Progress to unstable surfaces (foam pad).
- Tandem Stance Heel Raises: Improves dynamic control.
3. Controlled Weight-Bearing
- Mini Squats (3x12 reps): Partial range, ensuring knee tracks over toes.
- Step-Ups (2x10 reps/side): Low height (4 to 6"), controlled eccentric phase.
Things to Avoid in Phase 2:
- Aggressive jumping/running.
- Sudden direction changes.
- Overstretching into eversion.
Progression Criteria to Phase 3:
Full pain-free weight-bearing.
Single-leg stance >30 sec without wobbling.
No swelling after exercise.
Phase 3: Functional Training (Weeks 6 to 12+)
Goals:
- Restore dynamic stability for sports/ADLs.
- Rebuild power, agility, and endurance.
- Prepare for full return to activity.
1. Advanced Balance & Proprioception
A. Wobble Board/BOSU Drills
- Single-Leg Balance (30 to 60 sec) → Add arm motions or ball tosses.
- Tilt-to-Catch: Partner tosses ball while you balance on uneven surface.
B. Dynamic Stability Drills
- Single-Leg Squat to Mini-Hop (3x8 reps/side): Small hops landing with control.
- Star Excursion Balance Test (SEBT): Reach drills to improve neuromuscular control.
2. Agility & Plyometrics
A. Lateral Movements
- Lateral Shuffles (3x30 sec): Low-impact → progress to resisted bands.
- Carioca Drills (3x20 yards): Cross-step agility for multidirectional stability.
B. Controlled Plyos
- Box Step-Ups → Depth Drops (2x6 reps): Start low (6 to 12"), focus on soft landing.
- Single-Leg Hops (3x5 reps/side): Forward/backward → progress to lateral hops.
3. Sport-Specific Drills
- Cutting Drills (45°→90° turns): Mimic game-direction changes.
- Throwing/Kicking Progressions: Gradually increase distance/intensity.
- Endurance: Interval runs (e.g., jog/sprint ratios) if needed for sport.
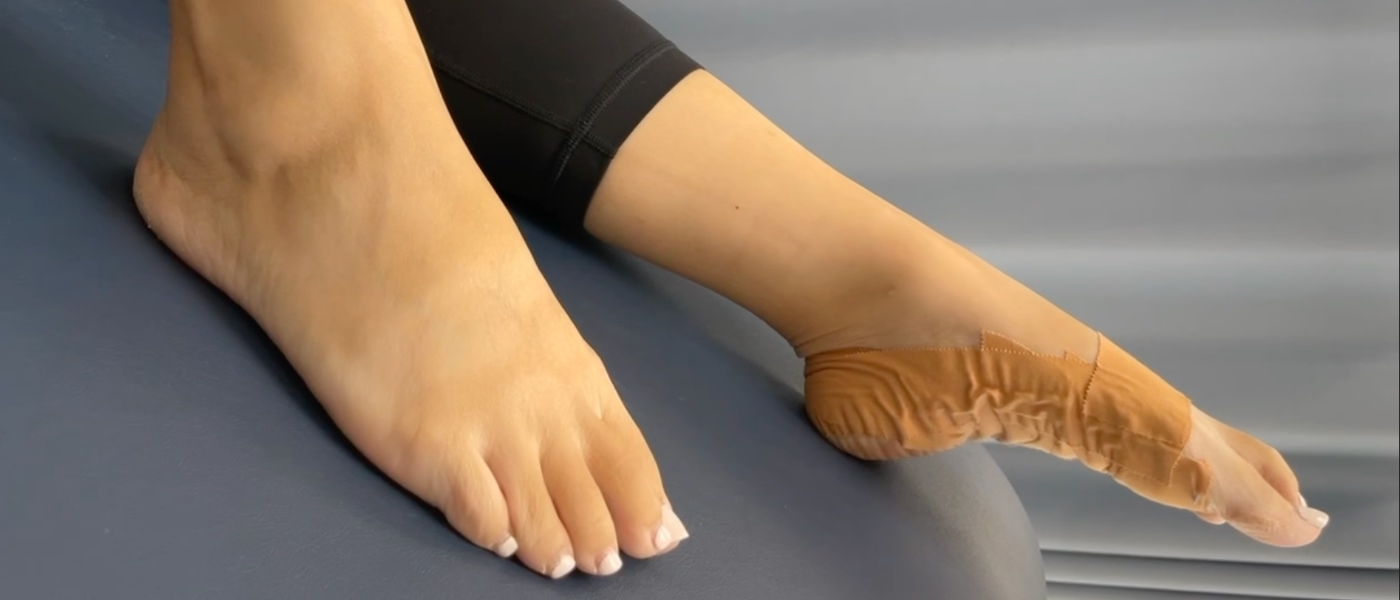
Taping and bracing may also be helpful for additional external support.
Avoid in Phase 3:
- Full-speed pivots/cutting without control.
- Max-effort jumps until cleared.
Progression Criteria to Phase 4 (Return to Sport):
No pain/swelling after high-impact drills.
90% strength/balance vs. uninjured side.
Passes sport-specific tests (e.g., hop tests, agility benchmarks).
Why Eversion Sprains Need Specialized Care
Eversion ankle sprains (medial/deltoid ligament injuries) require careful rehab due to:
- Higher Complication Risk - Greater likelihood of associated injuries (syndesmotic sprains, medial malleolus fractures)
- Severity - Results from high-force trauma that often damages multiple structures
- Healing Challenges - Poor blood supply to deep deltoid fibres leads to slower recovery (6-12+ weeks vs 2-6 weeks for lateral sprains)
- Unique Demands - Requires:
- Tibialis posterior strengthening
- Controlled pronation stability
- Hip/core integration
Unlike lateral sprains (focus on peroneals), eversion sprains need medial protection. Extended bracing (8-12 weeks) is often necessary during return to sport.
It is important to consider the combination of higher complication risk and slower healing for eversion sprains, as this means rushed rehab often leads to chronic instability.
Prognosis and Return to Activity
Recovery Timeline
- Grade I (Mild): 4 to 6 weeks
- Minimal ligament stretching
- Focus on early mobility and progressive strengthening
- Grade II (Moderate): 6 to 12 weeks
- Partial tearing of deltoid ligament
- Requires bracing and structured rehab
- Grade III (Severe): 3 to 6+ months
- Complete tear ± associated injuries (fractures/syndesmosis)
- May need surgery if unstable
Return to Sports
- Non-contact activities: 6 to 12 weeks (when strength/balance reaches 90% of uninjured side)
- Overhead/cutting sports: 3 to 6 months
- Requires sport-specific drills and gradual exposure to pivoting/impact
Key Factors Affecting Prognosis:
Early protection (avoid premature eversion stress)
Proper progression of strength/balance drills
Addressing kinetic chain deficits (hip/core/arch control)
Warning Signs of Poor Recovery:
Persistent medial pain
Feeling of "giving way"
Swelling after activity
Preventing Medial Ankle Injuries
- Proprioception Training
- Single-leg balance drills (progress to unstable surfaces)
- Wobble board/BOSU exercises 2-3x/week
- Targeted Strengthening
- Tibialis posterior focus: Banded inversions, heel raises on incline
- Peroneal balance: Resisted eversion to prevent overcompensation
- Footwear & Bracing
- Motion-control shoes for overpronators
- Prophylactic taping/bracing during high-risk activities
- Biomechanical Corrections
- Address overpronation with:
- Custom orthotics if needed
- Arch strengthening (towel scrunches, marble pickups)
- Improve hip/core stability (clamshells, dead bugs)
- Address overpronation with:
For Athletes:
Pre-season ankle strengthening program
Sport-specific agility drills (gradual exposure to cutting motions)
Taping for competition if history of sprains
Most Overlooked Factor:
Poor landing mechanics → Focus on soft, controlled landings during jump training
FAQs About Eversion Sprains
Can eversion sprains cause chronic instability?
Yes, if improperly rehabbed. The deltoid ligament’s poor blood supply slows healing, leading to:
- Persistent medial joint laxity
- Recurrent sprains or "giving way" sensations
- Increased risk of post-traumatic arthritis
- Prevention: 6+ weeks of bracing and eccentric tibialis posterior strengthening.
Eversion sprain vs. high ankle sprain
- Eversion sprain: Stretches/tears the deltoid ligament (medial side).
- High ankle sprain: Injures the syndesmotic ligaments (between tibia/fibula).
- Key distinction: High ankle sprains cause pain above the ankle and worsen with calf squeezes.
How is this different from a syndesmosis injury?
- Deltoid injury: Medial pain, swelling, eversion weakness.
- Syndesmosis injury:
- Pain with external rotation/dorsiflexion (e.g., squatting)
- Positive "squeeze test" (compressing calf elicits pain)
- Often requires longer rehab (3 to 6+ months).
When is surgery needed for a deltoid ligament tear?
Surgery is rare (10 to 15% of cases) but considered when:
- Grade III tear + ankle instability (failed 3+ months of rehab)
- Associated fractures (medial malleolus, syndesmotic disruption)
- Persistent pain/mechanical symptoms (e.g., catching, locking)
Post-op: 6 to 12 weeks non-weightbearing in a boot, then phased rehab.
What the Research Says
Medial (deltoid) ankle sprains are much less common than sprains on the outside of the ankle. A study of 25 US college sports recorded 380 deltoid ligament sprains over six seasons, a rate of 0.79 per 10,000 athlete exposures. Player contact caused about half of them (49.7%). Most were not long-term injuries: 72.9% needed less than one week of restriction, 6.6% were classed as severe, and 8.2% were repeat sprains. The authors note that deltoid sprains rarely happen on their own and can be overlooked when there is also a fracture (Kopec et al., 2017).
That link with other injuries matters. In a study of 64 athletes with a grade II high ankle sprain (syndesmosis injury) and no fracture, those who also had a deltoid ligament injury were 11 times as likely to have an unstable injury that needed surgical stabilization. Stable injuries returned to sport in an average of 45 days, while unstable injuries treated with surgery took an average of 64 days (Calder et al., 2016).
Key Takeaways
- Eversion (deltoid) sprains are less common than outer ankle sprains and are often caused by contact with another player.
- In college athletes, most deltoid sprains caused less than a week of restriction, but a small share were severe.
- A deltoid injury together with a high ankle sprain raises the chance that the ankle is unstable.
- A careful check for fractures and high ankle sprain is an important first step before rehab.
- Related pages: lateral ankle sprain, chronic ankle instability and posterior tibial tendinopathy.
Start Your Eversion Sprain Recovery Journey Today
Book a specialist assessment at Vaughan Physiotherapy Clinic to regain your strength and function!
Book Your Specialized Assessment Today:
- Phone: 905-669-1221
- Location: 398 Steeles Ave W #201, Thornhill, ON L4J 6X3
- Online Booking: www.vaughanphysiotherapy.com
Medial ankle sprains often come with other injuries, so a careful assessment is the first step. Our clinic is in Thornhill and Vaughan on Steeles Avenue West.
Convenient Thornhill and Vaughan location with evening/weekend appointments available.
By: Tiffany Corpus
References
Calder, J. D., Bamford, R., Petrie, A., & McCollum, G. A. (2016). Stable versus unstable grade II high ankle sprains: A prospective study predicting the need for surgical stabilization and time to return to sports. Arthroscopy, 32(4), 634-642. https://doi.org/10.1016/j.arthro.2015.10.003
Kopec, T. J., Hibberd, E. E., Roos, K. G., Djoko, A., Dompier, T. P., & Kerr, Z. Y. (2017). The epidemiology of deltoid ligament sprains in 25 National Collegiate Athletic Association sports, 2009-2010 through 2014-2015 academic years. Journal of Athletic Training, 52(4), 350-359. https://doi.org/10.4085/1062.6050-52.2.01







