



Physiotherapist performing hands-on myofascial release on a man's thigh to ease fascial adhesions and restrictions

Fascial Adhesions and Restrictions

Restrictions in connective tissue affecting mobility.

What Are Fascial Adhesions and Restrictions?

Fascial adhesions and restrictions refer to areas where the body's fascial network, a continuous web of connective tissue that surrounds and connects every muscle, bone, nerve, and organ, becomes stuck, thickened, or loses its ability to glide freely. Under normal conditions, healthy fascia is a supple, hydrated tissue that allows smooth movement between adjacent structures. When fascia becomes damaged through injury, surgery, chronic inflammation, or prolonged immobility, the tissue can develop abnormal cross-links and adhesions that bind layers together and restrict mobility.

These restrictions are far more than a surface-level stiffness. Research published in Life demonstrates that fascia mobility, especially along the shear planes that separate individual muscles, is critical for normal musculoskeletal function (Langevin, 2021). When adhesions form along these planes, they compromise not only range of motion but also proprioceptive awareness, the body's internal sense of position and movement. For many patients, fascial adhesions are the hidden driver behind persistent pain, recurring injuries, and movement patterns that fail to improve despite conventional strengthening and stretching exercises.

At Vaughan Physiotherapy, we specialize in identifying and treating fascial adhesions and restrictions, using hands-on care to ease symptoms and a progressive exercise plan to restore movement, helping patients in Thornhill and Vaughan and the greater Vaughan area restore pain-free movement and long-term functional health.

Anatomy of the Fascial System

Understanding fascial adhesions requires a basic appreciation of the fascial system itself. Fascia is not a single structure but a three-dimensional matrix of connective tissue that extends uninterrupted from head to toe. A landmark consensus statement published in the British Journal of Sports Medicine describes fascia as a body-wide tensional network that transmits mechanical forces, provides structural support, and plays an active role in proprioception and pain signaling (Zugel et al., 2018).

The fascial system is organized into several functional layers:

  • Superficial fascia sits just beneath the skin and contains adipose tissue, nerves, and blood vessels. It allows the skin to move freely over deeper structures and acts as a shock absorber during impacts and sustained pressure.
  • Deep fascia is a denser, more organized layer that envelops muscles, bones, and joints. It forms compartments that guide force transmission and help coordinate multi-joint movements. The deep fascia is richly innervated with mechanoreceptors and nociceptors, which means changes in its tension or integrity are directly communicated to the central nervous system.
  • Visceral fascia surrounds internal organs, providing support and allowing limited movement during breathing, digestion, and changes in posture.

Between these layers, and between individual fascial planes, lies loose connective tissue rich in hyaluronic acid. This substance acts as a lubricant, enabling the smooth gliding that is essential for efficient movement. Research in Bioengineering has shown that when hyaluronic acid becomes aggregated or dehydrated, the loose connective tissue loses its lubrication, and adjacent fascial layers begin to adhere to one another (Kodama et al., 2023). This is the fundamental mechanism behind fascial densification and, eventually, adhesion formation.

The fascial system also contains an extensive network of fibroblasts, cells responsible for producing and maintaining the collagen matrix. Under mechanical stress, fibroblasts can transform into myofibroblasts, contractile cells that actively shorten the tissue. Kodama et al. (2023) documented that this transformation can cause "gradual and irreversible tissue contraction as the contraction cycle is repeated many times," explaining why chronic fascial restrictions often feel progressively tighter over months and years.

Causes of Fascial Adhesions and Restrictions

Fascial adhesions develop through several interconnected pathways, and understanding these causes is essential for effective prevention and treatment.

  • Trauma and injury
  • Any direct blow, muscle tear, ligament sprain, or fracture triggers an inflammatory healing response. While inflammation is necessary for repair, excessive or prolonged inflammatory signaling leads to disorganized collagen deposition and scar tissue that binds fascial layers together. The consensus statement by Zugel et al. (2018) distinguishes between two pathological processes: densification, which involves alterations of the loose connective tissue between fascial layers, and fibrosis, which involves changes to the collagen fibrous bundles themselves. Both reduce tissue extensibility and compromise force transmission.
  • Surgical procedures
  • Post-surgical adhesions are among the most common and clinically significant forms of fascial restriction. Incisions cut through multiple fascial planes, and the healing process frequently produces adhesions that tether tissues across anatomical boundaries. Research confirms moderate to strong evidence that soft tissue mobilization techniques are effective for both acute post-surgical and chronic post-surgical adhesions.
  • Repetitive strain and overuse
  • Sustained postures, repetitive workplace movements, and sport-specific training loads can overwhelm the fascia's capacity to adapt. Over time, fibroblasts respond to chronic mechanical overload by producing excess collagen, leading to tissue thickening and reduced flexibility. This is particularly common in desk workers who maintain static postures for hours daily, as well as in athletes who repetitively load specific movement patterns without adequate recovery.
  • Chronic inflammation
  • Systemic inflammatory conditions, metabolic disorders, and even prolonged psychological stress can alter the fascial environment. Inflammatory mediators change the viscosity of the ground substance, promote fibroblast proliferation, and disrupt the normal turnover of collagen, all of which contribute to progressive tissue stiffening and adhesion formation.
  • Prolonged immobility
  • Whether from bed rest, casting, or a sedentary lifestyle, lack of movement is one of the most potent triggers for fascial adhesion. Without regular mechanical loading, the hyaluronic acid between fascial layers loses its fluid properties, cross-links form between collagen fibres, and the tissue gradually loses its ability to stretch and glide. Studies show that fascial changes from immobility can begin within days and become increasingly difficult to reverse as time progresses.
  • Aging
  • Age-related fascial changes are well documented. Kodama et al. (2023) found that fascial thickness in the lower extremities decreases by 12 to 25 percent with aging, while the lumbar region shows a paradoxical increase of 40 to 76 percent, changes associated with increased stiffness, reduced mobility, and greater vulnerability to injury.

Start Your Journey to 

‍Better Health Today

Recover faster, move better, and feel stronger with expert physiotherapy. Our team is here to guide you every step of the way.

Why Physiotherapy Is Essential for Fascial Adhesions

Fascial adhesions rarely resolve on their own. Unlike acute muscle strains that follow a predictable healing timeline, fascial restrictions tend to become self-reinforcing: the adhesion limits movement, reduced movement further dehydrates the tissue, and the restriction progressively worsens. This cycle explains why many patients experience months or years of persistent tightness and pain that fails to respond to rest, stretching, or anti-inflammatory medications alone.

Physiotherapy is uniquely positioned to break this cycle for several important reasons.

  • Direct tissue mobilization
  • Physiotherapists trained in myofascial release and manual therapy techniques can apply sustained, targeted pressure to stiff or sore areas to ease pain and help the area move more freely in the short term. A randomized controlled trial published in the Journal of Clinical Medicine demonstrated that myofascial release increased blood flow in lumbar tissue by 31.6 percent immediately after treatment and by 48.7 percent at the 60-minute follow-up compared to placebo (Brandl et al., 2023). This is a short-term change. It may help comfort and make it easier to move, but it does not show that adhesions are reversed.
  • Comprehensive assessment
  • Fascial adhesions often present with symptoms that mimic other conditions, joint stiffness, nerve entrapment, muscle weakness, or referred pain. A physiotherapist conducts a thorough biomechanical assessment to identify the true source of restriction, differentiating fascial problems from joint, neural, or muscular pathology. This ensures treatment addresses the root cause rather than merely managing symptoms.
  • Progressive loading and rehabilitation Restoring fascial health requires more than passive treatment. Physiotherapists design individualized exercise programs that progressively reload the fascial system, stimulating healthy collagen remodeling and preventing re-adhesion. Hands-on work can make early sessions more comfortable, but exercise and graded loading do the main work over time.
  • Education and self-management
  • Long-term fascial health depends on understanding the behaviours and habits that contribute to adhesion formation. Physiotherapists educate patients on posture modification, movement variety, hydration, and self-myofascial release techniques that maintain treatment gains between sessions.

Recovery Timeline: What to Expect

Recovery from fascial adhesions varies considerably depending on the severity, duration, and underlying cause of the restriction. The following general timeline provides a framework for expectations, though individual results will differ.

  • Weeks 1 to 3: Initial relief and assessment During the first few treatment sessions, the primary goals are accurate diagnosis, pain reduction, and beginning to restore basic tissue mobility. Many patients experience noticeable improvement in pain and stiffness after two to three manual therapy sessions, as the initial layers of restriction are addressed and local blood flow improves. Research by Brandl et al. (2023) confirms that measurable microcirculation improvements occur immediately following myofascial release, supporting the early symptomatic relief patients commonly report.
  • Weeks 4 to 8: Active restoration
  • As superficial restrictions resolve, treatment progresses to address deeper fascial layers and more established adhesions. This phase incorporates increasing active exercise alongside manual therapy. Patients typically notice meaningful improvements in range of motion, movement quality, and functional capacity. The frequency of treatment sessions may begin to taper as home exercise programs become more central to the recovery plan.
  • Weeks 8 to 16: Remodeling and strengthening
  • Fascial tissue remodels more slowly than muscle, requiring sustained mechanical stimulus over weeks to months. During this phase, the focus shifts toward progressive loading, sport-specific or work-specific movement training, and addressing any compensatory patterns that developed during the period of restriction. Patients with post-surgical adhesions or long-standing chronic restrictions may require the full duration of this phase.

Ongoing maintenance. Fascia is a living tissue that responds continuously to mechanical load, hydration, and movement variety. Patients who have experienced significant fascial adhesions benefit from periodic maintenance sessions and consistent self-management practices to prevent recurrence.

Treatment Approaches for Fascial Adhesions at Vaughan Physiotherapy

Our treatment of fascial adhesions integrates multiple evidence-based approaches tailored to each patient's specific presentation and goals.

  • Myofascial release (MFR)
  • This hands-on technique involves applying sustained, low-load pressure to fascial restrictions until the tissue releases and elongates. A comprehensive review in the Journal of Multidisciplinary Healthcare reports that MFR may help pain and function in conditions including chronic low back pain, fibromyalgia, headache, and post-surgical restriction (Lv and Yin, 2024), although the quality of this research varies. We use it as a short-term helper to ease pain and stiffness so you can move and load the area with exercise, which does the main work.
  • Instrument-assisted soft tissue mobilization (IASTM)
  • Using specially designed stainless steel instruments, clinicians can detect and treat areas of fascial restriction with greater precision. The instruments amplify tactile feedback, allowing the therapist to identify subtle tissue changes and apply targeted treatment to specific adhesion sites.
  • Fascial manipulation
  • This systematic approach targets specific fascial densification points identified through careful assessment of movement patterns and pain distribution. Pilot research has demonstrated that fascial manipulation produces measurable decreases in densification thickness and significant pain reduction, with improvements confirmed on ultrasound imaging.
  • Active release techniques
  • Combining precise manual contact with specific patient movements, active release techniques address fascial adhesions dynamically, treating the restriction while the tissue is moving through its functional range. This approach is particularly effective for adhesions related to repetitive strain and overuse injuries.
  • Therapeutic exercise and movement training Progressive exercise is fundamental to lasting fascial health. Our programs incorporate multi-directional loading, eccentric strengthening, and movement variability to stimulate healthy fascial remodeling and prevent re-adhesion. The fascial system responds best to varied mechanical stimuli rather than repetitive, single-plane exercises.
  • Dry needling
  • For deep fascial restrictions that are difficult to access through surface-level manual techniques, dry needling may be used to ease pain and muscle tension in the short term, so you can move and exercise more comfortably.
  • Education and self-myofascial release
  • We teach patients foam rolling, ball work, and stretching techniques designed specifically for fascial tissue. These self-management tools are essential for maintaining treatment gains and represent the cornerstone of long-term fascial health.

Preventing Fascial Adhesions and Restrictions

While some causes of fascial adhesion, surgery, acute trauma, cannot always be avoided, many fascial restrictions are preventable through consistent attention to movement, posture, and tissue health.

  • Move frequently and variably
  • The single most important factor in fascial health is regular, varied movement. Fascia thrives on multi-directional loading and deteriorates under static postures. Aim to change position at least every 30 to 45 minutes during sedentary work, and incorporate activities that challenge the body through multiple planes of motion, swimming, yoga, dance, or martial arts alongside traditional strengthening exercises.
  • Stay hydrated
  • The ground substance between fascial layers depends on adequate hydration to maintain its lubricating properties. Chronic dehydration contributes to increased fascial stiffness and greater susceptibility to adhesion formation.
  • Address injuries promptly
  • Early physiotherapy intervention after injury or surgery can significantly reduce the extent of fascial adhesion formation. Controlled, progressive movement during the healing process helps ensure that new collagen is laid down in organized patterns rather than forming disorganized scar tissue.
  • Incorporate self-myofascial release
  • Regular foam rolling or ball work, even five to ten minutes daily, helps maintain fascial hydration, promotes inter-layer gliding, and can identify developing restrictions before they become symptomatic.
  • Manage stress and sleep
  • Chronic psychological stress elevates inflammatory markers and increases fascial tension through sustained muscle guarding. Adequate sleep supports tissue repair and collagen remodeling, both essential for fascial health.
  • Warm up dynamically
  • Before physical activity, dynamic warm-ups that move joints through full ranges of motion prepare the fascial system for load by increasing tissue temperature, improving hydration, and activating the neuromuscular connections that depend on healthy fascial proprioception.

Frequently Asked Questions About Fascial Adhesions and Restrictions

  • How do I know if I have fascial adhesions rather than a muscle or joint problem?
  • Fascial adhesions often present as a diffuse tightness or pulling sensation that does not correspond to a single muscle or joint. The restriction may affect movement in multiple directions and may feel like a "stuck" or "bound" quality rather than sharp pain. A physiotherapist can differentiate fascial restrictions from joint or muscular problems through specific assessment techniques including palpation, movement analysis, and, when indicated, ultrasound imaging. Research confirms that diagnostic ultrasound can effectively visualize fascial pathology including thickness changes, altered echogenicity, and reduced tissue gliding (Kodama et al., 2023).
  • Is myofascial release painful?
  • Myofascial release typically involves sustained pressure that may produce a deep, stretching sensation or mild discomfort, but it should not be acutely painful. The technique is applied gradually, allowing the tissue time to release naturally. Most patients describe the sensation as "good pain", uncomfortable but relieving. If treatment ever becomes too intense, the pressure can be adjusted immediately. Post-treatment soreness similar to that following a deep massage is common for 24 to 48 hours.
  • How many physiotherapy sessions will I need for fascial adhesions?
  • The number of sessions depends on the severity, duration, and cause of the adhesions. Mild, recent restrictions may respond within four to six sessions, while long-standing or post-surgical adhesions typically require eight to sixteen sessions over two to four months. Your physiotherapist will establish a treatment plan with clear milestones and regularly reassess progress. Active participation in home exercises significantly accelerates recovery and reduces the total number of clinic visits required.
  • Can fascial adhesions come back after treatment?
  • Yes, fascial adhesions can recur if the underlying contributing factors are not addressed. This is why comprehensive physiotherapy goes beyond passive treatment to include exercise prescription, postural education, and self-management strategies. Patients who maintain regular movement variety, self-myofascial release practices, and appropriate workload management have significantly lower recurrence rates. Periodic maintenance sessions can also help identify and address developing restrictions before they become symptomatic.
  • What is the difference between fascial densification and fascial fibrosis?
  • Densification and fibrosis represent two distinct but related pathological changes in fascial tissue. Densification refers to alterations in the loose connective tissue between fascial layers, the hyaluronic acid-rich ground substance becomes aggregated, losing its lubricating properties and causing adjacent layers to adhere. Fibrosis involves changes to the collagen fibrous bundles themselves, with excess collagen deposition creating a thickened, stiffened tissue structure (Zugel et al., 2018). Densification is generally more reversible with manual therapy, while fibrosis may require more prolonged treatment and progressive mechanical loading to remodel.
  • Are fascial adhesions the same as trigger points?
  • While related, fascial adhesions and trigger points are distinct phenomena. Trigger points are hypersensitive nodules within taut bands of muscle that produce local and referred pain when compressed. Fascial adhesions are areas where fascial layers have become bound together, restricting gliding and movement. However, trigger points often develop in association with fascial restrictions, when fascial adhesions limit tissue mobility, the resulting mechanical stress on muscle fibres can activate trigger points. Effective treatment frequently addresses both conditions simultaneously. A comprehensive review notes that trigger points in muscle bands play central roles in pain generation across diverse musculoskeletal pathologies (Lv and Yin, 2024).
  • Can I treat fascial adhesions at home, or do I need professional treatment?
  • Self-myofascial release using foam rollers, lacrosse balls, or massage guns can be effective for mild fascial tightness and as a maintenance strategy. However, more significant adhesions, particularly those resulting from surgery, trauma, or prolonged immobility, generally require professional assessment and hands-on treatment. A physiotherapist can access deeper fascial layers, apply more precise techniques, and design a progressive rehabilitation program that addresses the full scope of the restriction. The most effective approach combines professional treatment with consistent home self-management.

What the Research Says

Hands-on fascial techniques are widely used, but the research on them is still thin. A systematic review of myofascial release for chronic musculoskeletal pain found 8 randomized trials covering tennis elbow, fibromyalgia, low back pain and heel pain. Only three of the trials had a low risk of bias, and in the low back pain and fibromyalgia trials the gains in pain and disability were smaller than the change patients usually notice as meaningful. The authors concluded that current evidence is not enough to support myofascial release as a treatment for chronic musculoskeletal pain (Laimi et al., 2018).

Self-treatment shows a similar picture. A meta-analysis of 21 studies found that foam rolling before exercise gave a small short-term gain in flexibility (about 4%), and rolling after exercise eased perceived muscle soreness. The authors judged the overall effects to be minor, and better suited to a warm-up than to recovery (Wiewelhove et al., 2019).

In practice, this points to how physiotherapy works best: hands-on and self-release techniques are short-term helpers for comfort and flexibility, while exercise and gradual loading do the main work.

Related pages: scar tissue and adhesion management, myofascial trigger point pain and postural myofascial syndromes.

Key Takeaways

  • Fascia is the connective tissue that wraps and links muscles, and stiffness or poor gliding between layers can follow injury, surgery or long periods without movement.
  • Research on myofascial release for chronic pain is limited and mixed, so it works best as part of a plan rather than on its own.
  • Foam rolling gives small short-term gains in flexibility and can ease soreness.
  • Regular, varied movement and progressive exercise are the backbone of long-term improvement.

Take the First Step Toward Pain-Free Movement

Fascial adhesions and restrictions do not have to limit your life. Whether you are dealing with post-surgical stiffness, chronic tightness from a sedentary lifestyle, or persistent pain that has not responded to other treatments, our team at Vaughan Physiotherapy can help.

Our physiotherapists look at how load moves through the whole region, use hands-on care as a short-term helper for comfort and movement, and build an exercise and graded loading plan that does the main work, so you can move, perform, and recover with less pain.

Book your assessment today:

Your fascia connects everything. Let us help you move freely again.

References

Laimi, K., Makila, A., Barlund, E., Katajapuu, N., Oksanen, A., Seikkula, V., Karppinen, J., & Saltychev, M. (2018). Effectiveness of myofascial release in treatment of chronic musculoskeletal pain: A systematic review. Clinical Rehabilitation, 32(4), 440 to 450. https://doi.org/10.1177/0269215517732820

Wiewelhove, T., Döweling, A., Schneider, C., Hottenrott, L., Meyer, T., Kellmann, M., Pfeiffer, M., & Ferrauti, A. (2019). A meta-analysis of the effects of foam rolling on performance and recovery. Frontiers in Physiology, 10, 376. https://doi.org/10.3389/fphys.2019.00376

Team

Condition guide

Fascial Adhesions and Restrictions

Restrictions in connective tissue affecting mobility.
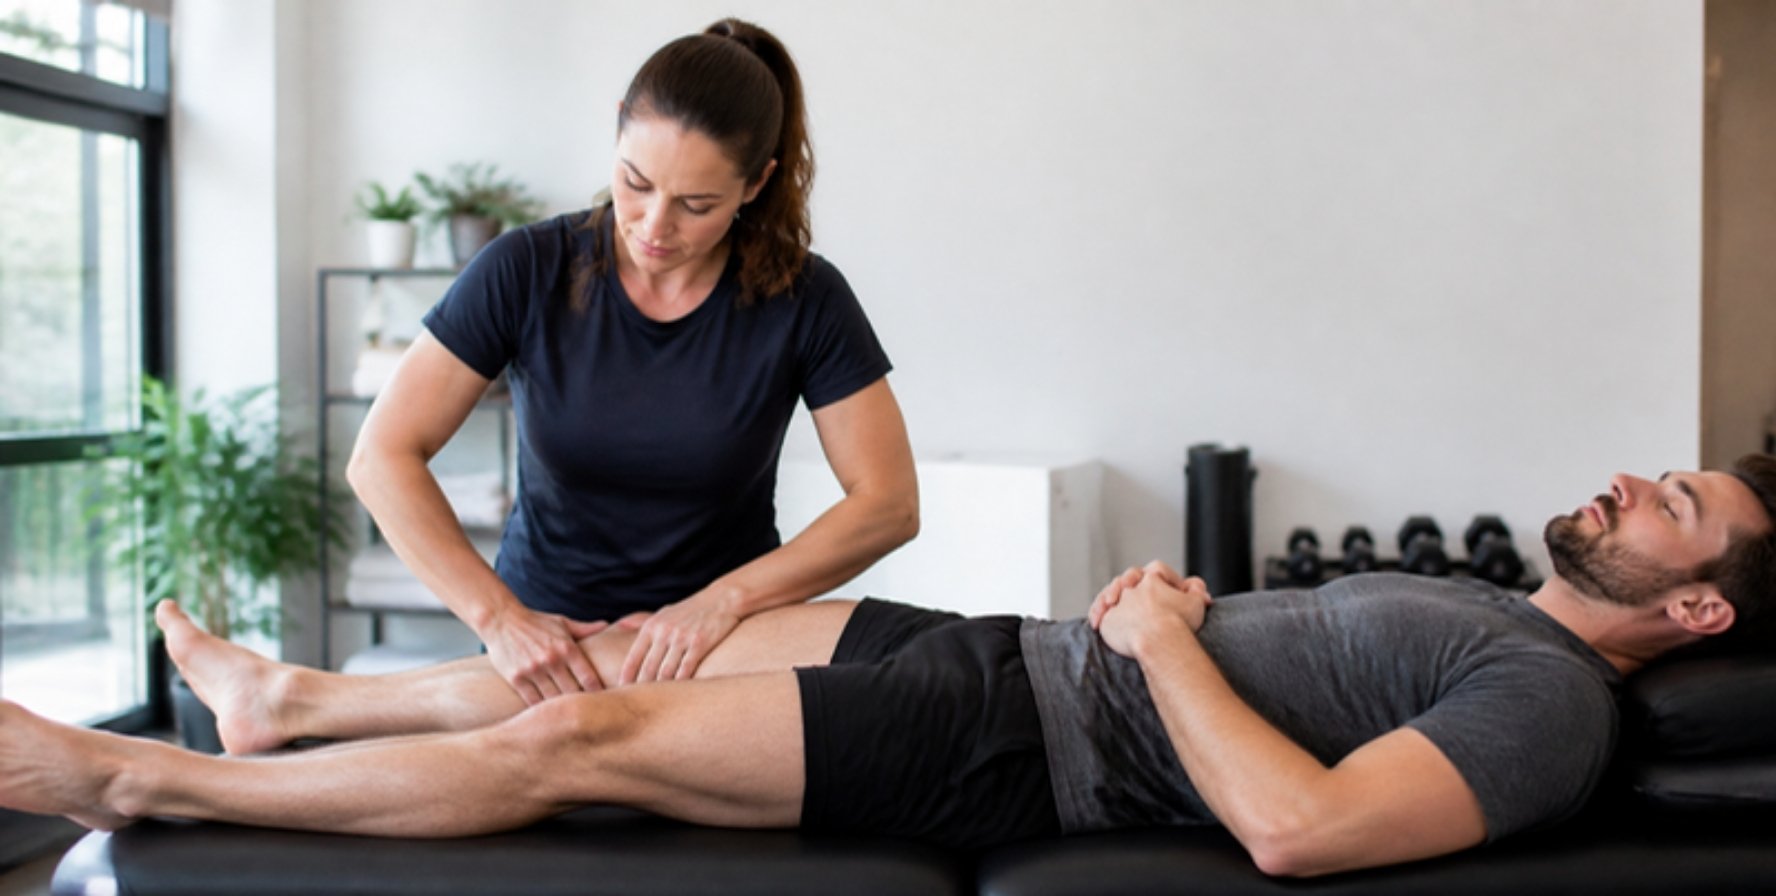
Physiotherapist performing hands-on myofascial release on a man's thigh to ease fascial adhesions and restrictionsFascial Adhesions and Restrictions

What Are Fascial Adhesions and Restrictions?

Fascial adhesions and restrictions refer to areas where the body's fascial network, a continuous web of connective tissue that surrounds and connects every muscle, bone, nerve, and organ, becomes stuck, thickened, or loses its ability to glide freely. Under normal conditions, healthy fascia is a supple, hydrated tissue that allows smooth movement between adjacent structures. When fascia becomes damaged through injury, surgery, chronic inflammation, or prolonged immobility, the tissue can develop abnormal cross-links and adhesions that bind layers together and restrict mobility.

These restrictions are far more than a surface-level stiffness. Research published in Life demonstrates that fascia mobility, especially along the shear planes that separate individual muscles, is critical for normal musculoskeletal function (Langevin, 2021). When adhesions form along these planes, they compromise not only range of motion but also proprioceptive awareness, the body's internal sense of position and movement. For many patients, fascial adhesions are the hidden driver behind persistent pain, recurring injuries, and movement patterns that fail to improve despite conventional strengthening and stretching exercises.

At Vaughan Physiotherapy, we specialize in identifying and treating fascial adhesions and restrictions, using hands-on care to ease symptoms and a progressive exercise plan to restore movement, helping patients in Thornhill and Vaughan and the greater Vaughan area restore pain-free movement and long-term functional health.

Anatomy of the Fascial System

Understanding fascial adhesions requires a basic appreciation of the fascial system itself. Fascia is not a single structure but a three-dimensional matrix of connective tissue that extends uninterrupted from head to toe. A landmark consensus statement published in the British Journal of Sports Medicine describes fascia as a body-wide tensional network that transmits mechanical forces, provides structural support, and plays an active role in proprioception and pain signaling (Zugel et al., 2018).

The fascial system is organized into several functional layers:

  • Superficial fascia sits just beneath the skin and contains adipose tissue, nerves, and blood vessels. It allows the skin to move freely over deeper structures and acts as a shock absorber during impacts and sustained pressure.
  • Deep fascia is a denser, more organized layer that envelops muscles, bones, and joints. It forms compartments that guide force transmission and help coordinate multi-joint movements. The deep fascia is richly innervated with mechanoreceptors and nociceptors, which means changes in its tension or integrity are directly communicated to the central nervous system.
  • Visceral fascia surrounds internal organs, providing support and allowing limited movement during breathing, digestion, and changes in posture.

Between these layers, and between individual fascial planes, lies loose connective tissue rich in hyaluronic acid. This substance acts as a lubricant, enabling the smooth gliding that is essential for efficient movement. Research in Bioengineering has shown that when hyaluronic acid becomes aggregated or dehydrated, the loose connective tissue loses its lubrication, and adjacent fascial layers begin to adhere to one another (Kodama et al., 2023). This is the fundamental mechanism behind fascial densification and, eventually, adhesion formation.

The fascial system also contains an extensive network of fibroblasts, cells responsible for producing and maintaining the collagen matrix. Under mechanical stress, fibroblasts can transform into myofibroblasts, contractile cells that actively shorten the tissue. Kodama et al. (2023) documented that this transformation can cause "gradual and irreversible tissue contraction as the contraction cycle is repeated many times," explaining why chronic fascial restrictions often feel progressively tighter over months and years.

Causes of Fascial Adhesions and Restrictions

Fascial adhesions develop through several interconnected pathways, and understanding these causes is essential for effective prevention and treatment.

  • Trauma and injury
  • Any direct blow, muscle tear, ligament sprain, or fracture triggers an inflammatory healing response. While inflammation is necessary for repair, excessive or prolonged inflammatory signaling leads to disorganized collagen deposition and scar tissue that binds fascial layers together. The consensus statement by Zugel et al. (2018) distinguishes between two pathological processes: densification, which involves alterations of the loose connective tissue between fascial layers, and fibrosis, which involves changes to the collagen fibrous bundles themselves. Both reduce tissue extensibility and compromise force transmission.
  • Surgical procedures
  • Post-surgical adhesions are among the most common and clinically significant forms of fascial restriction. Incisions cut through multiple fascial planes, and the healing process frequently produces adhesions that tether tissues across anatomical boundaries. Research confirms moderate to strong evidence that soft tissue mobilization techniques are effective for both acute post-surgical and chronic post-surgical adhesions.
  • Repetitive strain and overuse
  • Sustained postures, repetitive workplace movements, and sport-specific training loads can overwhelm the fascia's capacity to adapt. Over time, fibroblasts respond to chronic mechanical overload by producing excess collagen, leading to tissue thickening and reduced flexibility. This is particularly common in desk workers who maintain static postures for hours daily, as well as in athletes who repetitively load specific movement patterns without adequate recovery.
  • Chronic inflammation
  • Systemic inflammatory conditions, metabolic disorders, and even prolonged psychological stress can alter the fascial environment. Inflammatory mediators change the viscosity of the ground substance, promote fibroblast proliferation, and disrupt the normal turnover of collagen, all of which contribute to progressive tissue stiffening and adhesion formation.
  • Prolonged immobility
  • Whether from bed rest, casting, or a sedentary lifestyle, lack of movement is one of the most potent triggers for fascial adhesion. Without regular mechanical loading, the hyaluronic acid between fascial layers loses its fluid properties, cross-links form between collagen fibres, and the tissue gradually loses its ability to stretch and glide. Studies show that fascial changes from immobility can begin within days and become increasingly difficult to reverse as time progresses.
  • Aging
  • Age-related fascial changes are well documented. Kodama et al. (2023) found that fascial thickness in the lower extremities decreases by 12 to 25 percent with aging, while the lumbar region shows a paradoxical increase of 40 to 76 percent, changes associated with increased stiffness, reduced mobility, and greater vulnerability to injury.

Why Physiotherapy Is Essential for Fascial Adhesions

Fascial adhesions rarely resolve on their own. Unlike acute muscle strains that follow a predictable healing timeline, fascial restrictions tend to become self-reinforcing: the adhesion limits movement, reduced movement further dehydrates the tissue, and the restriction progressively worsens. This cycle explains why many patients experience months or years of persistent tightness and pain that fails to respond to rest, stretching, or anti-inflammatory medications alone.

Physiotherapy is uniquely positioned to break this cycle for several important reasons.

  • Direct tissue mobilization
  • Physiotherapists trained in myofascial release and manual therapy techniques can apply sustained, targeted pressure to stiff or sore areas to ease pain and help the area move more freely in the short term. A randomized controlled trial published in the Journal of Clinical Medicine demonstrated that myofascial release increased blood flow in lumbar tissue by 31.6 percent immediately after treatment and by 48.7 percent at the 60-minute follow-up compared to placebo (Brandl et al., 2023). This is a short-term change. It may help comfort and make it easier to move, but it does not show that adhesions are reversed.
  • Comprehensive assessment
  • Fascial adhesions often present with symptoms that mimic other conditions, joint stiffness, nerve entrapment, muscle weakness, or referred pain. A physiotherapist conducts a thorough biomechanical assessment to identify the true source of restriction, differentiating fascial problems from joint, neural, or muscular pathology. This ensures treatment addresses the root cause rather than merely managing symptoms.
  • Progressive loading and rehabilitation Restoring fascial health requires more than passive treatment. Physiotherapists design individualized exercise programs that progressively reload the fascial system, stimulating healthy collagen remodeling and preventing re-adhesion. Hands-on work can make early sessions more comfortable, but exercise and graded loading do the main work over time.
  • Education and self-management
  • Long-term fascial health depends on understanding the behaviours and habits that contribute to adhesion formation. Physiotherapists educate patients on posture modification, movement variety, hydration, and self-myofascial release techniques that maintain treatment gains between sessions.

Recovery Timeline: What to Expect

Recovery from fascial adhesions varies considerably depending on the severity, duration, and underlying cause of the restriction. The following general timeline provides a framework for expectations, though individual results will differ.

  • Weeks 1 to 3: Initial relief and assessment During the first few treatment sessions, the primary goals are accurate diagnosis, pain reduction, and beginning to restore basic tissue mobility. Many patients experience noticeable improvement in pain and stiffness after two to three manual therapy sessions, as the initial layers of restriction are addressed and local blood flow improves. Research by Brandl et al. (2023) confirms that measurable microcirculation improvements occur immediately following myofascial release, supporting the early symptomatic relief patients commonly report.
  • Weeks 4 to 8: Active restoration
  • As superficial restrictions resolve, treatment progresses to address deeper fascial layers and more established adhesions. This phase incorporates increasing active exercise alongside manual therapy. Patients typically notice meaningful improvements in range of motion, movement quality, and functional capacity. The frequency of treatment sessions may begin to taper as home exercise programs become more central to the recovery plan.
  • Weeks 8 to 16: Remodeling and strengthening
  • Fascial tissue remodels more slowly than muscle, requiring sustained mechanical stimulus over weeks to months. During this phase, the focus shifts toward progressive loading, sport-specific or work-specific movement training, and addressing any compensatory patterns that developed during the period of restriction. Patients with post-surgical adhesions or long-standing chronic restrictions may require the full duration of this phase.

Ongoing maintenance. Fascia is a living tissue that responds continuously to mechanical load, hydration, and movement variety. Patients who have experienced significant fascial adhesions benefit from periodic maintenance sessions and consistent self-management practices to prevent recurrence.

Treatment Approaches for Fascial Adhesions at Vaughan Physiotherapy

Our treatment of fascial adhesions integrates multiple evidence-based approaches tailored to each patient's specific presentation and goals.

  • Myofascial release (MFR)
  • This hands-on technique involves applying sustained, low-load pressure to fascial restrictions until the tissue releases and elongates. A comprehensive review in the Journal of Multidisciplinary Healthcare reports that MFR may help pain and function in conditions including chronic low back pain, fibromyalgia, headache, and post-surgical restriction (Lv and Yin, 2024), although the quality of this research varies. We use it as a short-term helper to ease pain and stiffness so you can move and load the area with exercise, which does the main work.
  • Instrument-assisted soft tissue mobilization (IASTM)
  • Using specially designed stainless steel instruments, clinicians can detect and treat areas of fascial restriction with greater precision. The instruments amplify tactile feedback, allowing the therapist to identify subtle tissue changes and apply targeted treatment to specific adhesion sites.
  • Fascial manipulation
  • This systematic approach targets specific fascial densification points identified through careful assessment of movement patterns and pain distribution. Pilot research has demonstrated that fascial manipulation produces measurable decreases in densification thickness and significant pain reduction, with improvements confirmed on ultrasound imaging.
  • Active release techniques
  • Combining precise manual contact with specific patient movements, active release techniques address fascial adhesions dynamically, treating the restriction while the tissue is moving through its functional range. This approach is particularly effective for adhesions related to repetitive strain and overuse injuries.
  • Therapeutic exercise and movement training Progressive exercise is fundamental to lasting fascial health. Our programs incorporate multi-directional loading, eccentric strengthening, and movement variability to stimulate healthy fascial remodeling and prevent re-adhesion. The fascial system responds best to varied mechanical stimuli rather than repetitive, single-plane exercises.
  • Dry needling
  • For deep fascial restrictions that are difficult to access through surface-level manual techniques, dry needling may be used to ease pain and muscle tension in the short term, so you can move and exercise more comfortably.
  • Education and self-myofascial release
  • We teach patients foam rolling, ball work, and stretching techniques designed specifically for fascial tissue. These self-management tools are essential for maintaining treatment gains and represent the cornerstone of long-term fascial health.

Preventing Fascial Adhesions and Restrictions

While some causes of fascial adhesion, surgery, acute trauma, cannot always be avoided, many fascial restrictions are preventable through consistent attention to movement, posture, and tissue health.

  • Move frequently and variably
  • The single most important factor in fascial health is regular, varied movement. Fascia thrives on multi-directional loading and deteriorates under static postures. Aim to change position at least every 30 to 45 minutes during sedentary work, and incorporate activities that challenge the body through multiple planes of motion, swimming, yoga, dance, or martial arts alongside traditional strengthening exercises.
  • Stay hydrated
  • The ground substance between fascial layers depends on adequate hydration to maintain its lubricating properties. Chronic dehydration contributes to increased fascial stiffness and greater susceptibility to adhesion formation.
  • Address injuries promptly
  • Early physiotherapy intervention after injury or surgery can significantly reduce the extent of fascial adhesion formation. Controlled, progressive movement during the healing process helps ensure that new collagen is laid down in organized patterns rather than forming disorganized scar tissue.
  • Incorporate self-myofascial release
  • Regular foam rolling or ball work, even five to ten minutes daily, helps maintain fascial hydration, promotes inter-layer gliding, and can identify developing restrictions before they become symptomatic.
  • Manage stress and sleep
  • Chronic psychological stress elevates inflammatory markers and increases fascial tension through sustained muscle guarding. Adequate sleep supports tissue repair and collagen remodeling, both essential for fascial health.
  • Warm up dynamically
  • Before physical activity, dynamic warm-ups that move joints through full ranges of motion prepare the fascial system for load by increasing tissue temperature, improving hydration, and activating the neuromuscular connections that depend on healthy fascial proprioception.

Frequently Asked Questions About Fascial Adhesions and Restrictions

  • How do I know if I have fascial adhesions rather than a muscle or joint problem?
  • Fascial adhesions often present as a diffuse tightness or pulling sensation that does not correspond to a single muscle or joint. The restriction may affect movement in multiple directions and may feel like a "stuck" or "bound" quality rather than sharp pain. A physiotherapist can differentiate fascial restrictions from joint or muscular problems through specific assessment techniques including palpation, movement analysis, and, when indicated, ultrasound imaging. Research confirms that diagnostic ultrasound can effectively visualize fascial pathology including thickness changes, altered echogenicity, and reduced tissue gliding (Kodama et al., 2023).
  • Is myofascial release painful?
  • Myofascial release typically involves sustained pressure that may produce a deep, stretching sensation or mild discomfort, but it should not be acutely painful. The technique is applied gradually, allowing the tissue time to release naturally. Most patients describe the sensation as "good pain", uncomfortable but relieving. If treatment ever becomes too intense, the pressure can be adjusted immediately. Post-treatment soreness similar to that following a deep massage is common for 24 to 48 hours.
  • How many physiotherapy sessions will I need for fascial adhesions?
  • The number of sessions depends on the severity, duration, and cause of the adhesions. Mild, recent restrictions may respond within four to six sessions, while long-standing or post-surgical adhesions typically require eight to sixteen sessions over two to four months. Your physiotherapist will establish a treatment plan with clear milestones and regularly reassess progress. Active participation in home exercises significantly accelerates recovery and reduces the total number of clinic visits required.
  • Can fascial adhesions come back after treatment?
  • Yes, fascial adhesions can recur if the underlying contributing factors are not addressed. This is why comprehensive physiotherapy goes beyond passive treatment to include exercise prescription, postural education, and self-management strategies. Patients who maintain regular movement variety, self-myofascial release practices, and appropriate workload management have significantly lower recurrence rates. Periodic maintenance sessions can also help identify and address developing restrictions before they become symptomatic.
  • What is the difference between fascial densification and fascial fibrosis?
  • Densification and fibrosis represent two distinct but related pathological changes in fascial tissue. Densification refers to alterations in the loose connective tissue between fascial layers, the hyaluronic acid-rich ground substance becomes aggregated, losing its lubricating properties and causing adjacent layers to adhere. Fibrosis involves changes to the collagen fibrous bundles themselves, with excess collagen deposition creating a thickened, stiffened tissue structure (Zugel et al., 2018). Densification is generally more reversible with manual therapy, while fibrosis may require more prolonged treatment and progressive mechanical loading to remodel.
  • Are fascial adhesions the same as trigger points?
  • While related, fascial adhesions and trigger points are distinct phenomena. Trigger points are hypersensitive nodules within taut bands of muscle that produce local and referred pain when compressed. Fascial adhesions are areas where fascial layers have become bound together, restricting gliding and movement. However, trigger points often develop in association with fascial restrictions, when fascial adhesions limit tissue mobility, the resulting mechanical stress on muscle fibres can activate trigger points. Effective treatment frequently addresses both conditions simultaneously. A comprehensive review notes that trigger points in muscle bands play central roles in pain generation across diverse musculoskeletal pathologies (Lv and Yin, 2024).
  • Can I treat fascial adhesions at home, or do I need professional treatment?
  • Self-myofascial release using foam rollers, lacrosse balls, or massage guns can be effective for mild fascial tightness and as a maintenance strategy. However, more significant adhesions, particularly those resulting from surgery, trauma, or prolonged immobility, generally require professional assessment and hands-on treatment. A physiotherapist can access deeper fascial layers, apply more precise techniques, and design a progressive rehabilitation program that addresses the full scope of the restriction. The most effective approach combines professional treatment with consistent home self-management.

What the Research Says

Hands-on fascial techniques are widely used, but the research on them is still thin. A systematic review of myofascial release for chronic musculoskeletal pain found 8 randomized trials covering tennis elbow, fibromyalgia, low back pain and heel pain. Only three of the trials had a low risk of bias, and in the low back pain and fibromyalgia trials the gains in pain and disability were smaller than the change patients usually notice as meaningful. The authors concluded that current evidence is not enough to support myofascial release as a treatment for chronic musculoskeletal pain (Laimi et al., 2018).

Self-treatment shows a similar picture. A meta-analysis of 21 studies found that foam rolling before exercise gave a small short-term gain in flexibility (about 4%), and rolling after exercise eased perceived muscle soreness. The authors judged the overall effects to be minor, and better suited to a warm-up than to recovery (Wiewelhove et al., 2019).

In practice, this points to how physiotherapy works best: hands-on and self-release techniques are short-term helpers for comfort and flexibility, while exercise and gradual loading do the main work.

Related pages: scar tissue and adhesion management, myofascial trigger point pain and postural myofascial syndromes.

Key Takeaways

  • Fascia is the connective tissue that wraps and links muscles, and stiffness or poor gliding between layers can follow injury, surgery or long periods without movement.
  • Research on myofascial release for chronic pain is limited and mixed, so it works best as part of a plan rather than on its own.
  • Foam rolling gives small short-term gains in flexibility and can ease soreness.
  • Regular, varied movement and progressive exercise are the backbone of long-term improvement.

Take the First Step Toward Pain-Free Movement

Fascial adhesions and restrictions do not have to limit your life. Whether you are dealing with post-surgical stiffness, chronic tightness from a sedentary lifestyle, or persistent pain that has not responded to other treatments, our team at Vaughan Physiotherapy can help.

Our physiotherapists look at how load moves through the whole region, use hands-on care as a short-term helper for comfort and movement, and build an exercise and graded loading plan that does the main work, so you can move, perform, and recover with less pain.

Book your assessment today:

Your fascia connects everything. Let us help you move freely again.

References

Laimi, K., Makila, A., Barlund, E., Katajapuu, N., Oksanen, A., Seikkula, V., Karppinen, J., & Saltychev, M. (2018). Effectiveness of myofascial release in treatment of chronic musculoskeletal pain: A systematic review. Clinical Rehabilitation, 32(4), 440 to 450. https://doi.org/10.1177/0269215517732820

Wiewelhove, T., Döweling, A., Schneider, C., Hottenrott, L., Meyer, T., Kellmann, M., Pfeiffer, M., & Ferrauti, A. (2019). A meta-analysis of the effects of foam rolling on performance and recovery. Frontiers in Physiology, 10, 376. https://doi.org/10.3389/fphys.2019.00376

How it works

Getting started.

  1. 01

    No referral needed

    You can book directly. Some benefit plans ask for a doctor's note, so check yours before your visit.

  2. 02

    Your first assessment, 45 minutes

    Your history, movement testing, a clear diagnosis and a plan you understand.

  3. 03

    Follow-up sessions

    Hands-on care and exercise, progressed each visit.

  4. 04

    Not the right fit? Second opinion on us

    If you're not satisfied with your initial assessment, a second assessment with another therapist is complimentary.

Who treats this

Clinicians who treat this.

Tap a profile for credentials and booking.

Not sure this is what you have?

One of our therapists can check what is going on and build a plan around what they find. Book online, or call us at 905-669-1221.