



Therapist massaging the upper shoulder and neck muscles of a man lying face down on a treatment table

Myofascial Trigger Point Headaches

Headaches caused or worsened by sensitive knots (trigger points) in the neck, shoulder, scalp, and jaw muscles that refer pain into the head.
Do you get a dull, band-like headache that seems to start in your neck or shoulders and creep up into your head? Do certain spots in your upper back, neck, or jaw feel sore and knotted, and does pressing on them bring on your familiar headache? If so, muscle trigger points may be playing a part in your headaches.

At Vaughan Physiotherapy Clinic, we assess and treat headaches linked to tight, tender muscles in the head, neck, and jaw for desk workers, students, drivers, athletes, and anyone who has started to plan their day around their next headache. The goal is not just to rub out a knot for a day or two, but to understand why those muscles keep getting overloaded and to build a plan that reduces how often and how hard your headaches hit.

Here is what myofascial trigger point headaches are, how to recognize them, what they can be confused with, and what the research says about treating them.

What Are Myofascial Trigger Point Headaches?

A myofascial trigger point is a very sensitive spot inside a muscle, usually found within a tight band of muscle fibres. Pressing on it is painful, and it can send pain to another area, which is called referred pain (Do et al., 2018). When trigger points in the head, neck, or jaw muscles refer pain into the head, they can produce or add to a headache.

"Myofascial trigger point headache" is a practical, descriptive term rather than a separate official diagnosis. In the international headache classification, the closest match is tension-type headache, which is the most common headache type. Lifetime estimates range from about 30 to 78 percent of people across studies, and tenderness in the muscles around the skull is described as the most important abnormal finding in this headache type (Headache Classification Committee of the International Headache Society, 2018).

Trigger points are also found more often in people with migraine than in people without headaches, and active trigger points are rare in people who do not get headaches (Do et al., 2018). Researchers are still working out whether trigger points cause headaches, result from repeated headaches, or both. The current view is that sensitive muscles and a sensitized nervous system likely feed into each other (Do et al., 2018).

Active and Latent Trigger Points

Trigger points are usually described in two ways (Do et al., 2018):

  • Active trigger points: cause ongoing pain on their own, and pressing on them reproduces your usual headache
  • Latent trigger points: are tender only when pressed, and do not cause pain at rest

In studies of tension-type headache, pressing on trigger points brought on referred head pain in most people with chronic headaches and in a smaller share of people with episodic headaches (Do et al., 2018).

Understanding the Anatomy

The muscles most often studied in trigger point headaches include (Do et al., 2018):

  • Upper trapezius: the muscle running from the base of the skull across the top of the shoulder
  • Suboccipital muscles: small, deep muscles that connect the skull to the top two neck bones
  • Sternocleidomastoid (SCM): the long muscle on the side of the neck that turns and tilts the head
  • Temporalis and masseter: jaw-closing muscles at the temples and cheeks, often involved in clenching and grinding
  • Superior oblique: a small eye muscle; trigger points here have been linked to a deep ache behind the eye that can spread to the forehead

Recognizing the Symptoms

Headaches linked to trigger points usually look like tension-type headaches. Common features include (Headache Classification Committee of the International Headache Society, 2018; Do et al., 2018):

  • A pressing or tightening feeling, often described as a band or a heavy weight, rather than a throbbing pain
  • Pain on both sides of the head, or spreading from the back of the head, temples, or behind the eyes
  • Mild to moderate intensity that does not get worse with ordinary activity such as walking or climbing stairs
  • Headaches lasting from 30 minutes to several days
  • Tender, knotted spots in the neck, shoulders, scalp, or jaw, and pressing on them brings on your familiar headache
  • Usually no nausea or vomiting, although mild sensitivity to light or sound can occur

What Makes It Worse?

  • Long periods in one position: hours at a desk, laptop, or phone, or long drives, with little movement or change of posture
  • Stress and poor sleep: both are commonly reported headache triggers and can increase muscle guarding
  • Jaw clenching or grinding: overloads the temporalis and masseter muscles
  • Low fitness and neck muscle endurance: exercise-based programs reduce headache pain in trials, suggesting weak or deconditioned muscles may play a role (Varangot-Reille et al., 2022)
  • Frequent painkiller use: taking headache medication on many days a month can make headaches more frequent, which is why a headache diary is recommended (Headache Classification Committee of the International Headache Society, 2018)

What Else Could It Be?

Several headache types overlap with trigger point headaches and need a different plan. Part of our assessment is sorting these out:

  • Migraine: usually throbbing, often on one side, moderate to severe, made worse by activity, and often with nausea or strong sensitivity to light and sound. Migraine and tension-type headache often occur in the same person (Headache Classification Committee of the International Headache Society, 2018)
  • Cervicogenic headache: headache that comes from a problem in the neck joints, typically one-sided and linked to reduced neck movement
  • Temporomandibular disorder (TMD): jaw joint or jaw muscle pain, clicking, or locking, with pain around the temple and ear
  • Medication overuse headache: daily or near-daily headaches in someone taking painkillers or headache medications very often
  • Occipital neuralgia: sharp, shooting, electric pain at the back of the head rather than a dull pressure
  • Secondary headaches: headaches caused by another medical problem, such as high blood pressure, infection, a blood vessel problem, or a mass. These are uncommon but important to rule out (Do et al., 2019)

When to See a Doctor First

Most headaches are not dangerous, but some warning signs need prompt medical attention. Researchers have grouped these red flags into a screening checklist (Do et al., 2019). Call 911 or go to the emergency department for a sudden, severe "worst ever" headache, or a headache with weakness, numbness, trouble speaking, confusion, or fainting. See your physician promptly if you have:

  • A headache with fever, a stiff neck, or feeling generally unwell
  • A headache with changes in vision, balance, speech, or strength
  • A new headache after age 65, or a new or clearly different headache pattern
  • Headaches that are steadily getting worse over days or weeks
  • A headache brought on by coughing, sneezing, straining, or exercise, or one that changes a lot with lying down or standing up
  • A headache that started after a head or neck injury
  • A history of cancer or a weakened immune system, or a new headache during pregnancy or after giving birth
  • A painful red eye with the headache

Our physiotherapists screen for these signs at your first visit, including questions about blood vessel warning signs in the neck, and will coordinate with your family physician if anything needs medical review before or alongside treatment.

Related reading: You may also find our guides to tension-type headaches, cervicogenic headaches, trigger point pain and occipital neuralgia helpful.

Start Your Journey to 

‍Better Health Today

Recover faster, move better, and feel stronger with expert physiotherapy. Our team is here to guide you every step of the way.

Why Physiotherapy Is Essential

Headaches linked to trigger points are partly a muscle problem and partly a sensitivity problem. Tender, overworked muscles in the neck, shoulders, and jaw send a steady stream of pain signals, and over time the nervous system can become more reactive to them (Do et al., 2018). Painkillers can take the edge off a single headache, but they do not change why those muscles keep getting overloaded, and taking them too often can make headaches more frequent.

An Ontario clinical practice guideline for persistent headaches with neck pain recommends education plus exercise as the core of care for tension-type headache, with multimodal care that combines joint mobilization, neck exercise, and posture correction as another option for chronic headaches. The same guideline is honest that these treatments offer small benefits, not cures (Côté et al., 2019).

Physiotherapy addresses the main drivers:

  • Sensitive muscles: hands-on trigger point treatment and needling to settle the tender spots that reproduce your headache
  • Neck and shoulder endurance: specific exercise for the deep neck and shoulder blade muscles that hold your head up all day
  • Daily habits: desk setup, screen time, driving, jaw clenching, sleep, and breaks
  • Medication patterns: using a headache diary to track triggers and spot painkiller overuse

Your Treatment Plan at Vaughan Physiotherapy Clinic

Phase 1: Assessment and Screening (Visit 1)

Your first visit focuses on understanding your headaches and making sure physiotherapy is the right fit. A full assessment includes:

  • Headache history: where the pain is, what it feels like, how often it happens, how long it lasts, and what you take for it
  • Red flag and medical screening: questions to rule out headaches that need a physician first, using a recognized red flag checklist (Do et al., 2019)
  • Neck blood vessel screening: an international framework guides physiotherapists to ask about and check for signs of rare blood vessel problems in the neck before any neck treatment (Rushton et al., 2023)
  • Muscle examination: careful pressure over the trapezius, suboccipital, sternocleidomastoid, temporalis, and jaw muscles to find which spots reproduce your headache. Tenderness of these muscles is the most consistent finding in tension-type headache (Headache Classification Committee of the International Headache Society, 2018)
  • Neck and jaw movement: range of motion, joint stiffness, and how your jaw opens and closes

We will also ask you to keep a headache diary for a few weeks. A diary helps separate tension-type headache from migraine, which often occur together and are treated differently, and helps catch medication overuse early (Headache Classification Committee of the International Headache Society, 2018).

Phase 2: Settling Pain and Sensitivity (Weeks 1 to 3)

Manual trigger point therapy uses techniques such as sustained pressure on the trigger point (ischemic compression), soft tissue release, positional release, and muscle energy techniques. A systematic review of seven randomized trials (316 people) found that these techniques, delivered over 5 to 24 sessions across 2 to 12 weeks, reduced how often headaches happened, how intense they were, and how long they lasted, in both tension-type headache and migraine. In tension-type headache, the average reduction was about 3.5 fewer headaches a month. The certainty of this evidence was rated low to very low, so the results are encouraging but not definitive (Falsiroli Maistrello et al., 2018).

Dry needling places a thin filament needle directly into a trigger point. A systematic review of 11 trials found that, in the short term, dry needling relieved headache pain about as well as other treatments, and improved headache-related disability more than the comparison treatments in tension-type and cervicogenic headache. Only 4 of the trials were high quality (Pourahmadi et al., 2021).

Other early strategies include:

  • Education: understanding how muscles, stress, sleep, and sensitivity interact, so headaches feel less unpredictable
  • Movement breaks: short, regular changes of position during desk work or driving
  • Jaw awareness: noticing and relaxing daytime clenching

Phase 3: Building Neck and Shoulder Strength (Weeks 3 to 8)

Exercise is the part of treatment with the strongest guideline support. For episodic and chronic tension-type headache, the Ontario guideline supports low-load endurance exercises for the deep neck and shoulder blade muscles, typically up to 8 sessions over 6 weeks, and for chronic headaches also supports a broader general exercise program with stretching, strengthening, and aerobic exercise (Côté et al., 2019). A meta-analysis of 19 studies found that strength training had a moderate effect on headache pain in tension-type headache, although the certainty of the evidence was very low (Varangot-Reille et al., 2022).

Neck and shoulder exercise
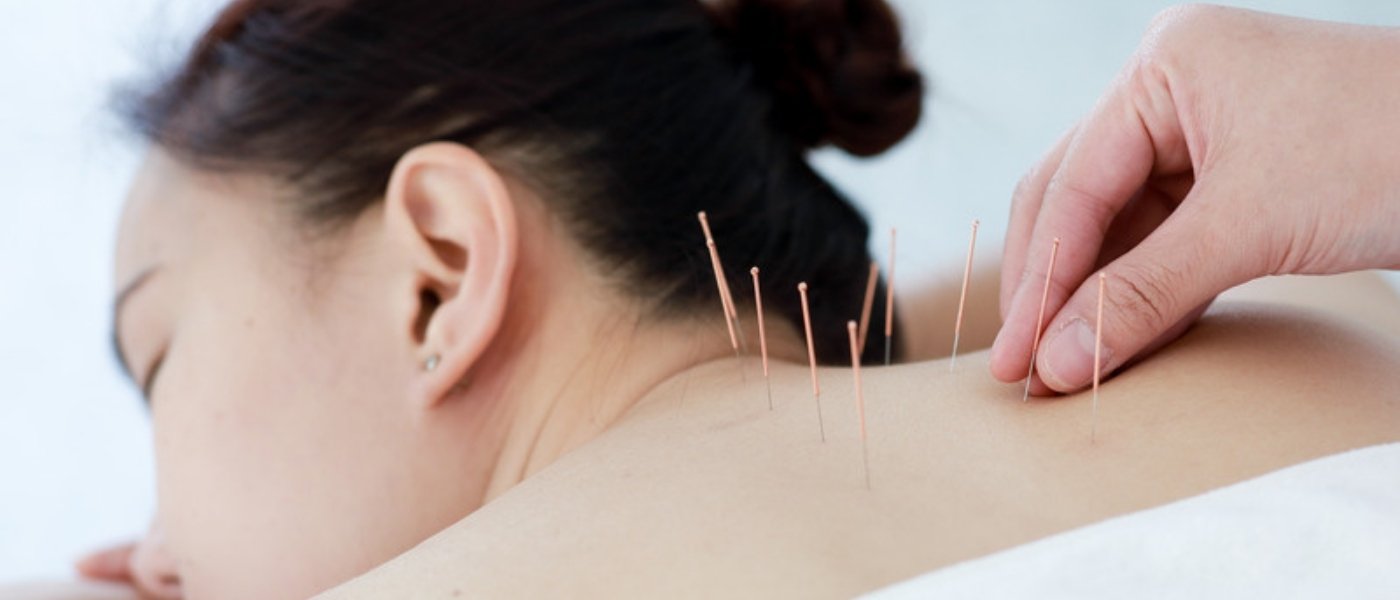
Practitioner placing fine needles in the upper back, neck and shoulder area of a woman lying face down
Dry needling may ease sensitive neck and shoulder muscles in the short term, while exercise builds longer lasting control.

Your program may include:

  • Chin nods (craniocervical flexion): a small, gentle nodding movement lying on your back to train the deep front neck muscles, progressed with holds and repetitions
  • Neck extensor endurance: controlled movements on hands and knees or sitting, keeping the neck in line
  • Shoulder blade exercises: rows, band pull-aparts, and wall slides to build the muscles that support the neck
  • Gentle stretches: for the upper trapezius, levator scapulae, and the chest, held comfortably and repeated through the day

General aerobic exercise

Regular walking, cycling, or swimming may reduce headache burden. Aerobic training has the clearest support in migraine, which often occurs alongside tension-type headache (Varangot-Reille et al., 2022).

Joint mobilization

Gentle mobilization of stiff neck and upper back joints can ease movement and pain. For chronic tension-type headache, the guideline supports it as part of a package with exercise and posture correction rather than on its own (Côté et al., 2019).

Phase 4: Long-Term Control and Self-Management (Weeks 8 to 12+)

  • Stepping down visits as you take over your own exercise and self-treatment
  • Self-release skills: using a ball or your hands to manage tender spots before they build into a headache
  • Workstation and driving review: screen height, chair setup, and break planning for your actual work day
  • A flare-up plan: what to do in the first hours of a headache, and when to come back for a tune-up

Beyond Physiotherapy: Complementary Care for Myofascial Trigger Point Headaches

Education, exercise, and hands-on care form the core of treatment for trigger point headaches. Some patients also benefit from other services at our clinic to ease pain and muscle tension so they can stay consistent with their program. Here is an honest summary of what the evidence does and does not show for each.

How Acupuncture and Dry Needling Can Help

Acupuncture and dry needling both use fine needles, but with different aims. Acupuncture uses traditional points, while dry needling targets trigger points directly.

  • What the evidence shows: a Cochrane review of 12 trials (2,349 adults) found acupuncture helpful for frequent episodic or chronic tension-type headache. About half of people had their headache days cut by at least half with acupuncture, compared with 43 percent with sham acupuncture, and the evidence was rated moderate quality (Linde et al., 2016). For dry needling, short-term disability improved more than with other treatments, but pain relief was similar to other treatments and most trials were small (Pourahmadi et al., 2021). The Ontario guideline found the acupuncture evidence for neck-related headache inconclusive (Côté et al., 2019)
  • Where it fits: as a way to settle stubborn trigger points and reduce headache frequency while you build strength and change daily habits
  • Safety: generally safe. In the Cochrane review, side effects were reported by 17 percent of people with acupuncture and 12 percent with sham, and they were usually minor, such as soreness or bruising at needle sites (Linde et al., 2016)

How Massage Therapy Can Help

Registered massage therapy can target trigger points in the neck, shoulders, scalp, and jaw.

  • What the evidence shows: in a randomized trial of 56 people with tension-type headache, 12 sessions of trigger point focused massage over 6 weeks reduced headache frequency and muscle tenderness, and people felt more improved than with placebo. However, headache frequency also dropped in the placebo group, and the difference between massage and placebo for frequency was not significant (Moraska et al., 2015). The Ontario guideline lists clinical massage as an option for chronic tension-type headache (Côté et al., 2019)
  • Where it fits: as a supportive treatment to ease tender, tight muscles, especially alongside an exercise program
  • Safety: very safe. Some temporary soreness after treatment is normal

How Chiropractic and Joint Manipulation Can Help

Chiropractic care for headaches uses joint mobilization and manipulation of the neck and upper back, often with soft tissue work.

  • What the evidence shows: the evidence depends on the type of headache. The Ontario guideline advises against neck manipulation as the only treatment for tension-type headache, but supports multimodal care that includes spinal mobilization, exercise, and posture correction for chronic tension-type headache. Manipulation of the neck and upper back is supported for cervicogenic headache, which comes from the neck joints (Côté et al., 2019)
  • Where it fits: for neck and upper back stiffness that seems to feed into your headaches, combined with exercise and trigger point care
  • Safety: generally safe when properly screened. Serious blood vessel problems in the neck are rare but important, which is why clinicians screen carefully before any neck manipulation (Rushton et al., 2023)

Whichever combination you and your clinician choose, these treatments share one purpose: calming sensitive muscles so you can keep up the exercise and daily changes that make the biggest long-term difference.

When Is Medical Treatment Needed?

Surgery is not a treatment for trigger point headaches. Some people do need medical care alongside physiotherapy, especially if headaches are frequent, severe, or mixed with migraine. Your family physician or a neurologist may discuss preventive medication, review your painkiller use, or offer trigger point injections. In tension-type headache, repeated local anaesthetic injections into trigger points reduced headache frequency and intensity compared with placebo in one study, while the benefit of botulinum toxin injections faded by 12 weeks in another (Do et al., 2018). We are happy to work with your physician and share our findings.

How Long Will It Take?

Every person is different, and results depend on how often your headaches happen, how long you have had them, and how much daily strain your neck and jaw are under. In the research, trigger point treatment programs ran from 2 to 12 weeks (Falsiroli Maistrello et al., 2018), and guideline-supported exercise programs ran about 6 weeks for neck endurance training and up to 12 weeks for general exercise (Côté et al., 2019).

In our experience, many people notice fewer or milder headaches within a few weeks, with steadier improvement over the following months as strength and habits change. Chronic headaches that have been present for years often take longer, and the goal is usually fewer and milder headaches rather than none at all.

Prevention and Long-Term Management

  • Keep your exercises going: a short neck and shoulder routine a few times a week helps hold your gains
  • Move often: change position regularly during desk work, study, or long drives
  • Set up your screens: bring screens to eye level and avoid long stretches looking down at a phone or laptop
  • Stay active: regular aerobic exercise you enjoy, built up gradually
  • Watch your jaw: notice clenching during the day, and talk to your dentist if you grind at night
  • Limit painkiller days: keep a diary and talk to your physician if you are taking headache medication often
  • Act early: use your self-release and exercises at the first sign of a building headache

Frequently Asked Questions

Are trigger point headaches the same as tension headaches?

They overlap a lot. Most headaches linked to trigger points fit the description of tension-type headache, although trigger points can also be present in people with migraine (Do et al., 2018).

Can trigger points cause migraines?

Trigger points are more common in people with migraine, and pressing on them can bring on an attack in some people. It is not yet clear whether they cause migraine or result from it (Do et al., 2018). Treating them may help some people with migraine, but migraine often also needs medical management.

Is it safe to treat my neck if I get headaches?

Yes, with proper screening. Our physiotherapists check for red flags and for rare blood vessel warning signs before any neck treatment (Rushton et al., 2023), and we choose gentle techniques if there is any doubt.

Why do I need exercises if massage makes me feel better?

Hands-on treatment can give quick relief, but the longer-term changes come from stronger, more resilient neck and shoulder muscles and better daily habits. Exercise and education are the core recommendations in current guidelines (Côté et al., 2019).

Can acupuncture, massage, or chiropractic replace exercise and self-management?

No. They can ease pain and muscle tension, and acupuncture has reasonable evidence for tension-type headache (Linde et al., 2016). But exercise, education, and daily habit changes are the foundation, and the other treatments work best as supports while you build those.

Will my headaches go away completely?

Some people become nearly headache-free, but for many the realistic goal is fewer, shorter, and milder headaches, with the confidence to manage a flare on your own. Research shows meaningful improvements on average, not guaranteed cures (Falsiroli Maistrello et al., 2018).

Our Specialized Approach at Vaughan Physiotherapy Clinic

Thorough headache assessment: we sort out which muscles, joints, and habits are driving your headaches, not just where it hurts

Hands-on trigger point care: manual release and dry needling for the tender spots that reproduce your headache

Neck and shoulder strengthening: guideline-based endurance exercise you can keep up at home

Desk, driving, and jaw habits: practical changes for your real work day

Integrated care: physiotherapy, massage therapy, acupuncture, and chiropractic under one roof when they add value

Safety first: red flag and neck blood vessel screening, with physician referral when needed

Take the First Step Toward Fewer Headaches

Headaches do not have to run your work day, your studies, or your weekends. Our team at Vaughan Physiotherapy Clinic helps patients from Thornhill, Vaughan, North York, Richmond Hill, and surrounding communities reduce headache frequency and take back control with evidence-based, hands-on care.

Book your assessment today:

Phone: 905-669-1221

Location: 398 Steeles Ave W #201, Thornhill, ON L4J 6X3

Online Booking: www.vaughanphysiotherapy.com

References

Côté P, Yu H, Shearer HM, et al. Non-pharmacological management of persistent headaches associated with neck pain: a clinical practice guideline from the Ontario Protocol for Traffic Injury Management (OPTIMa) collaboration. European Journal of Pain. 2019;23(6):1051-1070. doi:10.1002/ejp.1374

Do TP, Heldarskard GF, Kolding LT, Hvedstrup J, Schytz HW. Myofascial trigger points in migraine and tension-type headache. Journal of Headache and Pain. 2018;19(1):84. doi:10.1186/s10194-018-0913-8

Do TP, Remmers A, Schytz HW, et al. Red and orange flags for secondary headaches in clinical practice: SNNOOP10 list. Neurology. 2019;92(3):134-144. doi:10.1212/WNL.0000000000006697

Falsiroli Maistrello L, Geri T, Gianola S, Zaninetti M, Testa M. Effectiveness of trigger point manual treatment on the frequency, intensity, and duration of attacks in primary headaches: a systematic review and meta-analysis of randomized controlled trials. Frontiers in Neurology. 2018;9:254. doi:10.3389/fneur.2018.00254

Headache Classification Committee of the International Headache Society (IHS). The International Classification of Headache Disorders, 3rd edition. Cephalalgia. 2018;38(1):1-211. doi:10.1177/0333102417738202

Linde K, Allais G, Brinkhaus B, et al. Acupuncture for the prevention of tension-type headache. Cochrane Database of Systematic Reviews. 2016;4:CD007587. doi:10.1002/14651858.CD007587.pub2

Moraska AF, Stenerson L, Butryn N, Krutsch JP, Schmiege SJ, Mann JD. Myofascial trigger point-focused head and neck massage for recurrent tension-type headache: a randomized, placebo-controlled clinical trial. Clinical Journal of Pain. 2015;31(2):159-168. doi:10.1097/AJP.0000000000000091

Pourahmadi M, Dommerholt J, Fernández-de-Las-Peñas C, et al. Dry needling for the treatment of tension-type, cervicogenic, or migraine headaches: a systematic review and meta-analysis. Physical Therapy. 2021;101(5):pzab068. doi:10.1093/ptj/pzab068

Rushton A, Carlesso LC, Flynn T, et al. International framework for examination of the cervical region for potential of vascular pathologies of the neck prior to musculoskeletal intervention: International IFOMPT Cervical Framework. Journal of Orthopaedic & Sports Physical Therapy. 2023;53(1):7-22. doi:10.2519/jospt.2022.11147

Varangot-Reille C, Suso-Martí L, Romero-Palau M, Suárez-Pastor P, Cuenca-Martínez F. Effects of different therapeutic exercise modalities on migraine or tension-type headache: a systematic review and meta-analysis with a replicability analysis. Journal of Pain. 2022;23(7):1099-1122. doi:10.1016/j.jpain.2021.12.003

Disclaimer: This article is for educational purposes only and does not replace professional medical advice. Headaches can have many causes, including migraine, neck joint problems, medication overuse, and, rarely, serious medical conditions that need urgent care. If you have a sudden severe headache or any of the warning signs listed above, seek medical attention right away. Always consult a qualified healthcare provider for diagnosis and treatment specific to your condition.

Team

Condition guide

Myofascial Trigger Point Headaches

Headaches caused or worsened by sensitive knots (trigger points) in the neck, shoulder, scalp, and jaw muscles that refer pain into the head.

Therapist massaging the upper shoulder and neck muscles of a man lying face down on a treatment tableMyofascial Trigger Point Headaches

Do you get a dull, band-like headache that seems to start in your neck or shoulders and creep up into your head? Do certain spots in your upper back, neck, or jaw feel sore and knotted, and does pressing on them bring on your familiar headache? If so, muscle trigger points may be playing a part in your headaches.

At Vaughan Physiotherapy Clinic, we assess and treat headaches linked to tight, tender muscles in the head, neck, and jaw for desk workers, students, drivers, athletes, and anyone who has started to plan their day around their next headache. The goal is not just to rub out a knot for a day or two, but to understand why those muscles keep getting overloaded and to build a plan that reduces how often and how hard your headaches hit.

Here is what myofascial trigger point headaches are, how to recognize them, what they can be confused with, and what the research says about treating them.

What Are Myofascial Trigger Point Headaches?

A myofascial trigger point is a very sensitive spot inside a muscle, usually found within a tight band of muscle fibres. Pressing on it is painful, and it can send pain to another area, which is called referred pain (Do et al., 2018). When trigger points in the head, neck, or jaw muscles refer pain into the head, they can produce or add to a headache.

"Myofascial trigger point headache" is a practical, descriptive term rather than a separate official diagnosis. In the international headache classification, the closest match is tension-type headache, which is the most common headache type. Lifetime estimates range from about 30 to 78 percent of people across studies, and tenderness in the muscles around the skull is described as the most important abnormal finding in this headache type (Headache Classification Committee of the International Headache Society, 2018).

Trigger points are also found more often in people with migraine than in people without headaches, and active trigger points are rare in people who do not get headaches (Do et al., 2018). Researchers are still working out whether trigger points cause headaches, result from repeated headaches, or both. The current view is that sensitive muscles and a sensitized nervous system likely feed into each other (Do et al., 2018).

Active and Latent Trigger Points

Trigger points are usually described in two ways (Do et al., 2018):

  • Active trigger points: cause ongoing pain on their own, and pressing on them reproduces your usual headache
  • Latent trigger points: are tender only when pressed, and do not cause pain at rest

In studies of tension-type headache, pressing on trigger points brought on referred head pain in most people with chronic headaches and in a smaller share of people with episodic headaches (Do et al., 2018).

Understanding the Anatomy

The muscles most often studied in trigger point headaches include (Do et al., 2018):

  • Upper trapezius: the muscle running from the base of the skull across the top of the shoulder
  • Suboccipital muscles: small, deep muscles that connect the skull to the top two neck bones
  • Sternocleidomastoid (SCM): the long muscle on the side of the neck that turns and tilts the head
  • Temporalis and masseter: jaw-closing muscles at the temples and cheeks, often involved in clenching and grinding
  • Superior oblique: a small eye muscle; trigger points here have been linked to a deep ache behind the eye that can spread to the forehead

Recognizing the Symptoms

Headaches linked to trigger points usually look like tension-type headaches. Common features include (Headache Classification Committee of the International Headache Society, 2018; Do et al., 2018):

  • A pressing or tightening feeling, often described as a band or a heavy weight, rather than a throbbing pain
  • Pain on both sides of the head, or spreading from the back of the head, temples, or behind the eyes
  • Mild to moderate intensity that does not get worse with ordinary activity such as walking or climbing stairs
  • Headaches lasting from 30 minutes to several days
  • Tender, knotted spots in the neck, shoulders, scalp, or jaw, and pressing on them brings on your familiar headache
  • Usually no nausea or vomiting, although mild sensitivity to light or sound can occur

What Makes It Worse?

  • Long periods in one position: hours at a desk, laptop, or phone, or long drives, with little movement or change of posture
  • Stress and poor sleep: both are commonly reported headache triggers and can increase muscle guarding
  • Jaw clenching or grinding: overloads the temporalis and masseter muscles
  • Low fitness and neck muscle endurance: exercise-based programs reduce headache pain in trials, suggesting weak or deconditioned muscles may play a role (Varangot-Reille et al., 2022)
  • Frequent painkiller use: taking headache medication on many days a month can make headaches more frequent, which is why a headache diary is recommended (Headache Classification Committee of the International Headache Society, 2018)

What Else Could It Be?

Several headache types overlap with trigger point headaches and need a different plan. Part of our assessment is sorting these out:

  • Migraine: usually throbbing, often on one side, moderate to severe, made worse by activity, and often with nausea or strong sensitivity to light and sound. Migraine and tension-type headache often occur in the same person (Headache Classification Committee of the International Headache Society, 2018)
  • Cervicogenic headache: headache that comes from a problem in the neck joints, typically one-sided and linked to reduced neck movement
  • Temporomandibular disorder (TMD): jaw joint or jaw muscle pain, clicking, or locking, with pain around the temple and ear
  • Medication overuse headache: daily or near-daily headaches in someone taking painkillers or headache medications very often
  • Occipital neuralgia: sharp, shooting, electric pain at the back of the head rather than a dull pressure
  • Secondary headaches: headaches caused by another medical problem, such as high blood pressure, infection, a blood vessel problem, or a mass. These are uncommon but important to rule out (Do et al., 2019)

When to See a Doctor First

Most headaches are not dangerous, but some warning signs need prompt medical attention. Researchers have grouped these red flags into a screening checklist (Do et al., 2019). Call 911 or go to the emergency department for a sudden, severe "worst ever" headache, or a headache with weakness, numbness, trouble speaking, confusion, or fainting. See your physician promptly if you have:

  • A headache with fever, a stiff neck, or feeling generally unwell
  • A headache with changes in vision, balance, speech, or strength
  • A new headache after age 65, or a new or clearly different headache pattern
  • Headaches that are steadily getting worse over days or weeks
  • A headache brought on by coughing, sneezing, straining, or exercise, or one that changes a lot with lying down or standing up
  • A headache that started after a head or neck injury
  • A history of cancer or a weakened immune system, or a new headache during pregnancy or after giving birth
  • A painful red eye with the headache

Our physiotherapists screen for these signs at your first visit, including questions about blood vessel warning signs in the neck, and will coordinate with your family physician if anything needs medical review before or alongside treatment.

Related reading: You may also find our guides to tension-type headaches, cervicogenic headaches, trigger point pain and occipital neuralgia helpful.

Why Physiotherapy Is Essential

Headaches linked to trigger points are partly a muscle problem and partly a sensitivity problem. Tender, overworked muscles in the neck, shoulders, and jaw send a steady stream of pain signals, and over time the nervous system can become more reactive to them (Do et al., 2018). Painkillers can take the edge off a single headache, but they do not change why those muscles keep getting overloaded, and taking them too often can make headaches more frequent.

An Ontario clinical practice guideline for persistent headaches with neck pain recommends education plus exercise as the core of care for tension-type headache, with multimodal care that combines joint mobilization, neck exercise, and posture correction as another option for chronic headaches. The same guideline is honest that these treatments offer small benefits, not cures (Côté et al., 2019).

Physiotherapy addresses the main drivers:

  • Sensitive muscles: hands-on trigger point treatment and needling to settle the tender spots that reproduce your headache
  • Neck and shoulder endurance: specific exercise for the deep neck and shoulder blade muscles that hold your head up all day
  • Daily habits: desk setup, screen time, driving, jaw clenching, sleep, and breaks
  • Medication patterns: using a headache diary to track triggers and spot painkiller overuse

Your Treatment Plan at Vaughan Physiotherapy Clinic

Phase 1: Assessment and Screening (Visit 1)

Your first visit focuses on understanding your headaches and making sure physiotherapy is the right fit. A full assessment includes:

  • Headache history: where the pain is, what it feels like, how often it happens, how long it lasts, and what you take for it
  • Red flag and medical screening: questions to rule out headaches that need a physician first, using a recognized red flag checklist (Do et al., 2019)
  • Neck blood vessel screening: an international framework guides physiotherapists to ask about and check for signs of rare blood vessel problems in the neck before any neck treatment (Rushton et al., 2023)
  • Muscle examination: careful pressure over the trapezius, suboccipital, sternocleidomastoid, temporalis, and jaw muscles to find which spots reproduce your headache. Tenderness of these muscles is the most consistent finding in tension-type headache (Headache Classification Committee of the International Headache Society, 2018)
  • Neck and jaw movement: range of motion, joint stiffness, and how your jaw opens and closes

We will also ask you to keep a headache diary for a few weeks. A diary helps separate tension-type headache from migraine, which often occur together and are treated differently, and helps catch medication overuse early (Headache Classification Committee of the International Headache Society, 2018).

Phase 2: Settling Pain and Sensitivity (Weeks 1 to 3)

Manual trigger point therapy uses techniques such as sustained pressure on the trigger point (ischemic compression), soft tissue release, positional release, and muscle energy techniques. A systematic review of seven randomized trials (316 people) found that these techniques, delivered over 5 to 24 sessions across 2 to 12 weeks, reduced how often headaches happened, how intense they were, and how long they lasted, in both tension-type headache and migraine. In tension-type headache, the average reduction was about 3.5 fewer headaches a month. The certainty of this evidence was rated low to very low, so the results are encouraging but not definitive (Falsiroli Maistrello et al., 2018).

Dry needling places a thin filament needle directly into a trigger point. A systematic review of 11 trials found that, in the short term, dry needling relieved headache pain about as well as other treatments, and improved headache-related disability more than the comparison treatments in tension-type and cervicogenic headache. Only 4 of the trials were high quality (Pourahmadi et al., 2021).

Other early strategies include:

  • Education: understanding how muscles, stress, sleep, and sensitivity interact, so headaches feel less unpredictable
  • Movement breaks: short, regular changes of position during desk work or driving
  • Jaw awareness: noticing and relaxing daytime clenching

Phase 3: Building Neck and Shoulder Strength (Weeks 3 to 8)

Exercise is the part of treatment with the strongest guideline support. For episodic and chronic tension-type headache, the Ontario guideline supports low-load endurance exercises for the deep neck and shoulder blade muscles, typically up to 8 sessions over 6 weeks, and for chronic headaches also supports a broader general exercise program with stretching, strengthening, and aerobic exercise (Côté et al., 2019). A meta-analysis of 19 studies found that strength training had a moderate effect on headache pain in tension-type headache, although the certainty of the evidence was very low (Varangot-Reille et al., 2022).

Neck and shoulder exercise

Practitioner placing fine needles in the upper back, neck and shoulder area of a woman lying face down
Dry needling may ease sensitive neck and shoulder muscles in the short term, while exercise builds longer lasting control.

Your program may include:

  • Chin nods (craniocervical flexion): a small, gentle nodding movement lying on your back to train the deep front neck muscles, progressed with holds and repetitions
  • Neck extensor endurance: controlled movements on hands and knees or sitting, keeping the neck in line
  • Shoulder blade exercises: rows, band pull-aparts, and wall slides to build the muscles that support the neck
  • Gentle stretches: for the upper trapezius, levator scapulae, and the chest, held comfortably and repeated through the day

General aerobic exercise

Regular walking, cycling, or swimming may reduce headache burden. Aerobic training has the clearest support in migraine, which often occurs alongside tension-type headache (Varangot-Reille et al., 2022).

Joint mobilization

Gentle mobilization of stiff neck and upper back joints can ease movement and pain. For chronic tension-type headache, the guideline supports it as part of a package with exercise and posture correction rather than on its own (Côté et al., 2019).

Phase 4: Long-Term Control and Self-Management (Weeks 8 to 12+)

  • Stepping down visits as you take over your own exercise and self-treatment
  • Self-release skills: using a ball or your hands to manage tender spots before they build into a headache
  • Workstation and driving review: screen height, chair setup, and break planning for your actual work day
  • A flare-up plan: what to do in the first hours of a headache, and when to come back for a tune-up

Beyond Physiotherapy: Complementary Care for Myofascial Trigger Point Headaches

Education, exercise, and hands-on care form the core of treatment for trigger point headaches. Some patients also benefit from other services at our clinic to ease pain and muscle tension so they can stay consistent with their program. Here is an honest summary of what the evidence does and does not show for each.

How Acupuncture and Dry Needling Can Help

Acupuncture and dry needling both use fine needles, but with different aims. Acupuncture uses traditional points, while dry needling targets trigger points directly.

  • What the evidence shows: a Cochrane review of 12 trials (2,349 adults) found acupuncture helpful for frequent episodic or chronic tension-type headache. About half of people had their headache days cut by at least half with acupuncture, compared with 43 percent with sham acupuncture, and the evidence was rated moderate quality (Linde et al., 2016). For dry needling, short-term disability improved more than with other treatments, but pain relief was similar to other treatments and most trials were small (Pourahmadi et al., 2021). The Ontario guideline found the acupuncture evidence for neck-related headache inconclusive (Côté et al., 2019)
  • Where it fits: as a way to settle stubborn trigger points and reduce headache frequency while you build strength and change daily habits
  • Safety: generally safe. In the Cochrane review, side effects were reported by 17 percent of people with acupuncture and 12 percent with sham, and they were usually minor, such as soreness or bruising at needle sites (Linde et al., 2016)

How Massage Therapy Can Help

Registered massage therapy can target trigger points in the neck, shoulders, scalp, and jaw.

  • What the evidence shows: in a randomized trial of 56 people with tension-type headache, 12 sessions of trigger point focused massage over 6 weeks reduced headache frequency and muscle tenderness, and people felt more improved than with placebo. However, headache frequency also dropped in the placebo group, and the difference between massage and placebo for frequency was not significant (Moraska et al., 2015). The Ontario guideline lists clinical massage as an option for chronic tension-type headache (Côté et al., 2019)
  • Where it fits: as a supportive treatment to ease tender, tight muscles, especially alongside an exercise program
  • Safety: very safe. Some temporary soreness after treatment is normal

How Chiropractic and Joint Manipulation Can Help

Chiropractic care for headaches uses joint mobilization and manipulation of the neck and upper back, often with soft tissue work.

  • What the evidence shows: the evidence depends on the type of headache. The Ontario guideline advises against neck manipulation as the only treatment for tension-type headache, but supports multimodal care that includes spinal mobilization, exercise, and posture correction for chronic tension-type headache. Manipulation of the neck and upper back is supported for cervicogenic headache, which comes from the neck joints (Côté et al., 2019)
  • Where it fits: for neck and upper back stiffness that seems to feed into your headaches, combined with exercise and trigger point care
  • Safety: generally safe when properly screened. Serious blood vessel problems in the neck are rare but important, which is why clinicians screen carefully before any neck manipulation (Rushton et al., 2023)

Whichever combination you and your clinician choose, these treatments share one purpose: calming sensitive muscles so you can keep up the exercise and daily changes that make the biggest long-term difference.

When Is Medical Treatment Needed?

Surgery is not a treatment for trigger point headaches. Some people do need medical care alongside physiotherapy, especially if headaches are frequent, severe, or mixed with migraine. Your family physician or a neurologist may discuss preventive medication, review your painkiller use, or offer trigger point injections. In tension-type headache, repeated local anaesthetic injections into trigger points reduced headache frequency and intensity compared with placebo in one study, while the benefit of botulinum toxin injections faded by 12 weeks in another (Do et al., 2018). We are happy to work with your physician and share our findings.

How Long Will It Take?

Every person is different, and results depend on how often your headaches happen, how long you have had them, and how much daily strain your neck and jaw are under. In the research, trigger point treatment programs ran from 2 to 12 weeks (Falsiroli Maistrello et al., 2018), and guideline-supported exercise programs ran about 6 weeks for neck endurance training and up to 12 weeks for general exercise (Côté et al., 2019).

In our experience, many people notice fewer or milder headaches within a few weeks, with steadier improvement over the following months as strength and habits change. Chronic headaches that have been present for years often take longer, and the goal is usually fewer and milder headaches rather than none at all.

Prevention and Long-Term Management

  • Keep your exercises going: a short neck and shoulder routine a few times a week helps hold your gains
  • Move often: change position regularly during desk work, study, or long drives
  • Set up your screens: bring screens to eye level and avoid long stretches looking down at a phone or laptop
  • Stay active: regular aerobic exercise you enjoy, built up gradually
  • Watch your jaw: notice clenching during the day, and talk to your dentist if you grind at night
  • Limit painkiller days: keep a diary and talk to your physician if you are taking headache medication often
  • Act early: use your self-release and exercises at the first sign of a building headache

Frequently Asked Questions

Are trigger point headaches the same as tension headaches?

They overlap a lot. Most headaches linked to trigger points fit the description of tension-type headache, although trigger points can also be present in people with migraine (Do et al., 2018).

Can trigger points cause migraines?

Trigger points are more common in people with migraine, and pressing on them can bring on an attack in some people. It is not yet clear whether they cause migraine or result from it (Do et al., 2018). Treating them may help some people with migraine, but migraine often also needs medical management.

Is it safe to treat my neck if I get headaches?

Yes, with proper screening. Our physiotherapists check for red flags and for rare blood vessel warning signs before any neck treatment (Rushton et al., 2023), and we choose gentle techniques if there is any doubt.

Why do I need exercises if massage makes me feel better?

Hands-on treatment can give quick relief, but the longer-term changes come from stronger, more resilient neck and shoulder muscles and better daily habits. Exercise and education are the core recommendations in current guidelines (Côté et al., 2019).

Can acupuncture, massage, or chiropractic replace exercise and self-management?

No. They can ease pain and muscle tension, and acupuncture has reasonable evidence for tension-type headache (Linde et al., 2016). But exercise, education, and daily habit changes are the foundation, and the other treatments work best as supports while you build those.

Will my headaches go away completely?

Some people become nearly headache-free, but for many the realistic goal is fewer, shorter, and milder headaches, with the confidence to manage a flare on your own. Research shows meaningful improvements on average, not guaranteed cures (Falsiroli Maistrello et al., 2018).

Our Specialized Approach at Vaughan Physiotherapy Clinic

Thorough headache assessment: we sort out which muscles, joints, and habits are driving your headaches, not just where it hurts

Hands-on trigger point care: manual release and dry needling for the tender spots that reproduce your headache

Neck and shoulder strengthening: guideline-based endurance exercise you can keep up at home

Desk, driving, and jaw habits: practical changes for your real work day

Integrated care: physiotherapy, massage therapy, acupuncture, and chiropractic under one roof when they add value

Safety first: red flag and neck blood vessel screening, with physician referral when needed

Take the First Step Toward Fewer Headaches

Headaches do not have to run your work day, your studies, or your weekends. Our team at Vaughan Physiotherapy Clinic helps patients from Thornhill, Vaughan, North York, Richmond Hill, and surrounding communities reduce headache frequency and take back control with evidence-based, hands-on care.

Book your assessment today:

Phone: 905-669-1221

Location: 398 Steeles Ave W #201, Thornhill, ON L4J 6X3

Online Booking: www.vaughanphysiotherapy.com

References

Côté P, Yu H, Shearer HM, et al. Non-pharmacological management of persistent headaches associated with neck pain: a clinical practice guideline from the Ontario Protocol for Traffic Injury Management (OPTIMa) collaboration. European Journal of Pain. 2019;23(6):1051-1070. doi:10.1002/ejp.1374

Do TP, Heldarskard GF, Kolding LT, Hvedstrup J, Schytz HW. Myofascial trigger points in migraine and tension-type headache. Journal of Headache and Pain. 2018;19(1):84. doi:10.1186/s10194-018-0913-8

Do TP, Remmers A, Schytz HW, et al. Red and orange flags for secondary headaches in clinical practice: SNNOOP10 list. Neurology. 2019;92(3):134-144. doi:10.1212/WNL.0000000000006697

Falsiroli Maistrello L, Geri T, Gianola S, Zaninetti M, Testa M. Effectiveness of trigger point manual treatment on the frequency, intensity, and duration of attacks in primary headaches: a systematic review and meta-analysis of randomized controlled trials. Frontiers in Neurology. 2018;9:254. doi:10.3389/fneur.2018.00254

Headache Classification Committee of the International Headache Society (IHS). The International Classification of Headache Disorders, 3rd edition. Cephalalgia. 2018;38(1):1-211. doi:10.1177/0333102417738202

Linde K, Allais G, Brinkhaus B, et al. Acupuncture for the prevention of tension-type headache. Cochrane Database of Systematic Reviews. 2016;4:CD007587. doi:10.1002/14651858.CD007587.pub2

Moraska AF, Stenerson L, Butryn N, Krutsch JP, Schmiege SJ, Mann JD. Myofascial trigger point-focused head and neck massage for recurrent tension-type headache: a randomized, placebo-controlled clinical trial. Clinical Journal of Pain. 2015;31(2):159-168. doi:10.1097/AJP.0000000000000091

Pourahmadi M, Dommerholt J, Fernández-de-Las-Peñas C, et al. Dry needling for the treatment of tension-type, cervicogenic, or migraine headaches: a systematic review and meta-analysis. Physical Therapy. 2021;101(5):pzab068. doi:10.1093/ptj/pzab068

Rushton A, Carlesso LC, Flynn T, et al. International framework for examination of the cervical region for potential of vascular pathologies of the neck prior to musculoskeletal intervention: International IFOMPT Cervical Framework. Journal of Orthopaedic & Sports Physical Therapy. 2023;53(1):7-22. doi:10.2519/jospt.2022.11147

Varangot-Reille C, Suso-Martí L, Romero-Palau M, Suárez-Pastor P, Cuenca-Martínez F. Effects of different therapeutic exercise modalities on migraine or tension-type headache: a systematic review and meta-analysis with a replicability analysis. Journal of Pain. 2022;23(7):1099-1122. doi:10.1016/j.jpain.2021.12.003

Disclaimer: This article is for educational purposes only and does not replace professional medical advice. Headaches can have many causes, including migraine, neck joint problems, medication overuse, and, rarely, serious medical conditions that need urgent care. If you have a sudden severe headache or any of the warning signs listed above, seek medical attention right away. Always consult a qualified healthcare provider for diagnosis and treatment specific to your condition.

How it works

Getting started.

  1. 01

    No referral needed

    You can book directly. Some benefit plans ask for a doctor's note, so check yours before your visit.

  2. 02

    Your first assessment, 45 minutes

    Your history, movement testing, a clear diagnosis and a plan you understand.

  3. 03

    Follow-up sessions

    Hands-on care and exercise, progressed each visit.

  4. 04

    Not the right fit? Second opinion on us

    If you're not satisfied with your initial assessment, a second assessment with another therapist is complimentary.

Who treats this

Clinicians who treat this.

Tap a profile for credentials and booking.

Not sure this is what you have?

One of our therapists can check what is going on and build a plan around what they find. Book online, or call us at 905-669-1221.